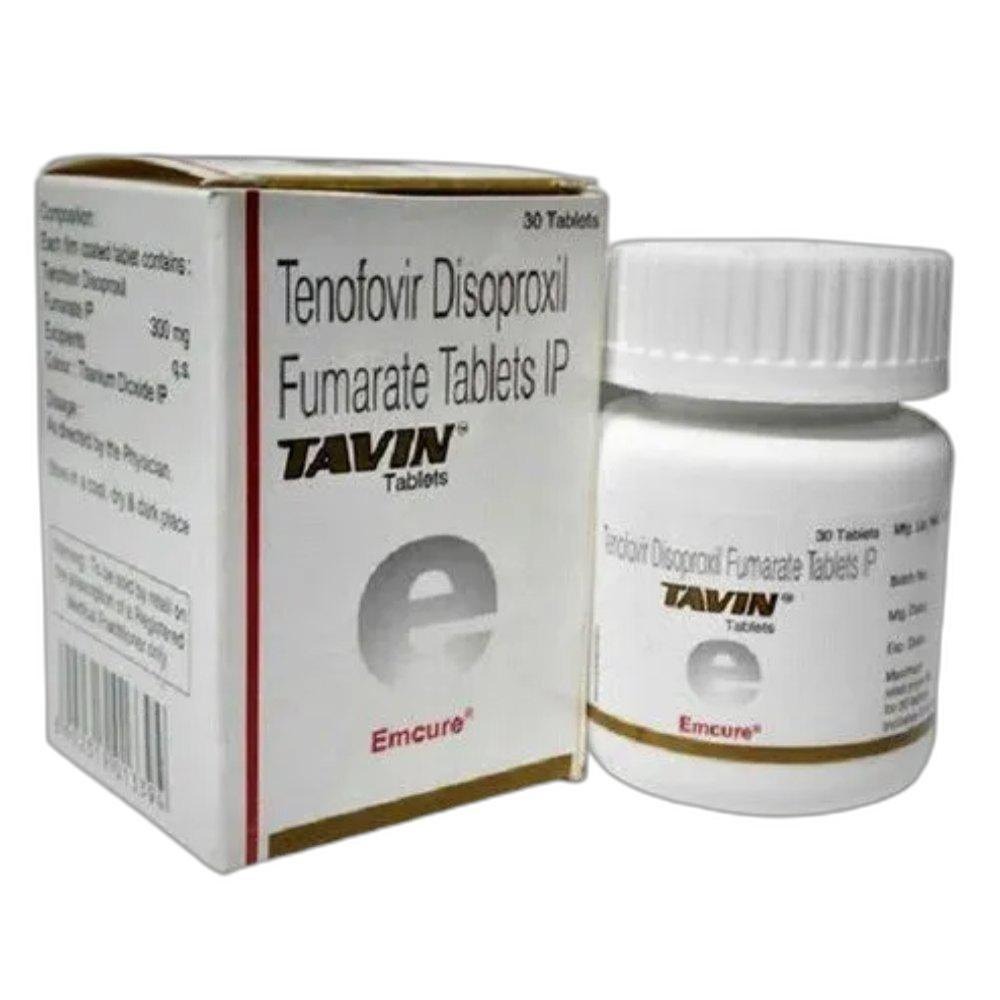
and Hepatitis B patient population across West Yorkshire — including significant South Asian communities from Leeds's Harehills and Chapeltown areas, East African and Caribbean communities, and Leeds's growing student population from across the world. Tavin TDF 300mg provides Leeds patients with affordable, proven antiviral therapy as part of combination HIV regimens or as standalone HBV treatment at dramatically reduced cost versus UK brand pricing.
Visit unnatipharmax.com | +91 82650 41513 | Unnatipharmax@gmail.com
 FAQ 1: How does Tenofovir DF (Tavin) work as part of HIV combination therapy in Leeds and why is it still widely used despite TAF's availability?
Tenofovir disoproxil fumarate (TDF) remains a cornerstone NRTI in HIV combination regimens globally, including at Leeds's St James's Hospital HIV clinic. TDF's mechanism: it is a prodrug converted intracellularly to tenofovir diphosphate (TFV-DP), which inhibits HIV reverse transcriptase by competing with deoxyadenosine triphosphate and, once incorporated into viral DNA, acting as a chain terminator. Despite TAF's superior renal and bone safety, TDF retains widespread use for several clinical and economic reasons. Clinical reasons: TDF achieves higher plasma tenofovir concentrations, which may be advantageous for certain co-infections and anatomical compartments (e.g., rectal mucosa — relevant for Leeds MSM on PrEP); genital fluid TDF concentrations appear higher than TAF, potentially relevant for female-to-male transmission prevention; and decades of safety and efficacy data in diverse populations underpin clinical confidence in TDF. Economic reasons: TDF is significantly cheaper than TAF in generic form — NHS prescribing guidelines still include TDF-based combinations as first-line options when cost-effectiveness is weighed against the marginal renal/bone benefit of TAF in patients without pre-existing kidney or bone problems. Leeds's St James's hospital pharmacists balance these considerations individually for each patient, switching to TAF (Tafsure) for patients showing TDF-related renal or bone changes while continuing Tavin for stable, young patients with normal renal function.
FAQ 2: How does Tavin TDF treat Hepatitis B in Leeds's South Asian population with HBV-related liver disease?Leeds's large Bangladeshi and Pakistani communities — concentrated in Harehills, Burmantofts, and Beeston — carry elevated Hepatitis B prevalence from perinatal and childhood transmission in South Asian countries of origin. HBV in Leeds's South Asian community often presents late — at the fibrosing or advanced hepatitis stage — because asymptomatic chronic HBV rarely prompts health-seeking in communities with limited awareness of HBV's long-term consequences. Tavin TDF 300mg is first-line HBV treatment at Leeds's St James's hepatology clinic for patients meeting treatment criteria (elevated ALT with significant viral replication, HBeAg-positive active hepatitis, or significant fibrosis on FibroScan). TDF inhibits HBV polymerase (an enzyme with reverse transcriptase activity) through the same mechanism as its HIV reverse transcriptase inhibition — TFV-DP incorporation terminates HBV DNA chain elongation. TDF produces HBV DNA suppression below 20 IU/mL (undetectable) in 90-95% of treated patients at 48 weeks — preventing the progressive hepatic inflammation that drives fibrosis, cirrhosis, and HCC. Leeds's South Asian HBV patients typically require lifelong Tavin treatment (unlike HCV which can be permanently cured) — making Unnati Pharmax's affordable pricing particularly relevant for this long-term treatment context.
FAQ 3: What renal monitoring protocol does St James's Leeds use for Tavin TDF patients and when is switching to TAF triggered?TDF's renal tubular toxicity — causing Fanconi syndrome and proximal renal tubular dysfunction in a minority of patients on long-term therapy — requires structured monitoring at Leeds's St James's HIV and hepatology clinics. Standard TDF monitoring protocol: eGFR and serum phosphate at baseline and every 3-6 months; urine protein:creatinine ratio and urine phosphate/glucose at 6-12 month intervals; DEXA bone density scan at baseline in patients with risk factors (older age, low BMI, steroid use, smoking) and annually or biannually thereafter. Triggers for switching from Tavin TDF to Tafsure TAF at St James's: eGFR decline below 60 mL/min or decline of more than 25% from baseline; urinary phosphate wasting (tubular reabsorption of phosphate below 85%); glycosuria without diabetes (proximal tubular glucose transport failure); bone density T-score below -2.5 (osteoporosis) or significant decline from baseline; and patient preference after informed discussion of renal/bone risk. Leeds's HIV clinicians perform this monitoring systematically — identifying TDF-related changes early when reversal by switching to Tafsure is most complete. For patients who remain on Tavin TDF without renal or bone changes, the switch to TAF is not mandated — Tavin's established efficacy and lower cost support its continued use in appropriate patients.
FAQ 4: How does Tavin TDF affect bone density in Leeds's older HIV-positive patients and what management is recommended?TDF causes measurable bone mineral density (BMD) reduction — approximately 2-3% decline in spine and hip BMD in the first 48 weeks of therapy, stabilising thereafter. This TDF-associated bone effect is compounded in HIV-positive patients by: HIV infection itself causing bone turnover dysregulation independent of ART; older age (Leeds's long-term HIV survivors, now in their 50s-60s, face age-related bone loss on top of TDF effects); smoking (prevalent in Leeds's HIV-affected communities); low vitamin D (endemic in Leeds's northern latitude population); and in men, hypogonadism related to HIV or its treatment. For Leeds's older Tavin TDF users at St James's, BMD management includes: calcium 1,000-1,200 mg/day and vitamin D 800-1,000 IU/day supplementation; smoking cessation support through Leeds's NHS Stop Smoking Services; exercise promotion — weight-bearing exercise at Leeds's leisure centres has been specifically advocated by the St James's HIV clinic; and in patients with T-score below -2.0 or significant fracture risk, bisphosphonate therapy (alendronate or zoledronic acid) in addition to or instead of TDF-to-TAF switching. Leeds's older HIV-positive patients represent a growing clinical challenge — the remarkable ART success that has allowed survival into older age now creates a complex intersection of HIV, ageing, and long-term medication effects that St James's comprehensive HIV care addresses.
FAQ 5: How does Leeds's large student population affect HIV and HBV treatment demand and what role does Tavin play?Leeds is one of England's largest student cities — the University of Leeds, Leeds Beckett, and Leeds Trinity collectively enrol over 60,000 students, including approximately 15,000 international students from HBV-endemic regions (China, South East Asia, Sub-Saharan Africa) and HIV-prevalent regions (Southern Africa). This large, transient population creates specific antiviral access challenges. International students: many arrive with known HBV or HIV diagnoses managed in their home countries; medication formulary differences (their home country ART regimen may not match NHS prescribing patterns); registration delays with Leeds GP practices mean treatment continuity gaps in the first weeks of term; and student health insurance (through universities or personal travel insurance) may not cover specialist antiviral medications. Leeds University's campus health services have dedicated international student health coordinators who assist with NHS registration and specialist referral. Tavin TDF from Unnati Pharmax serves Leeds's international student population during the critical first weeks in Leeds when NHS registration is pending — preventing the treatment interruptions that cause HBV reactivation or HIV viral rebound in students who arrive committed to their antiviral regimen but face administrative barriers to continuing it immediately.