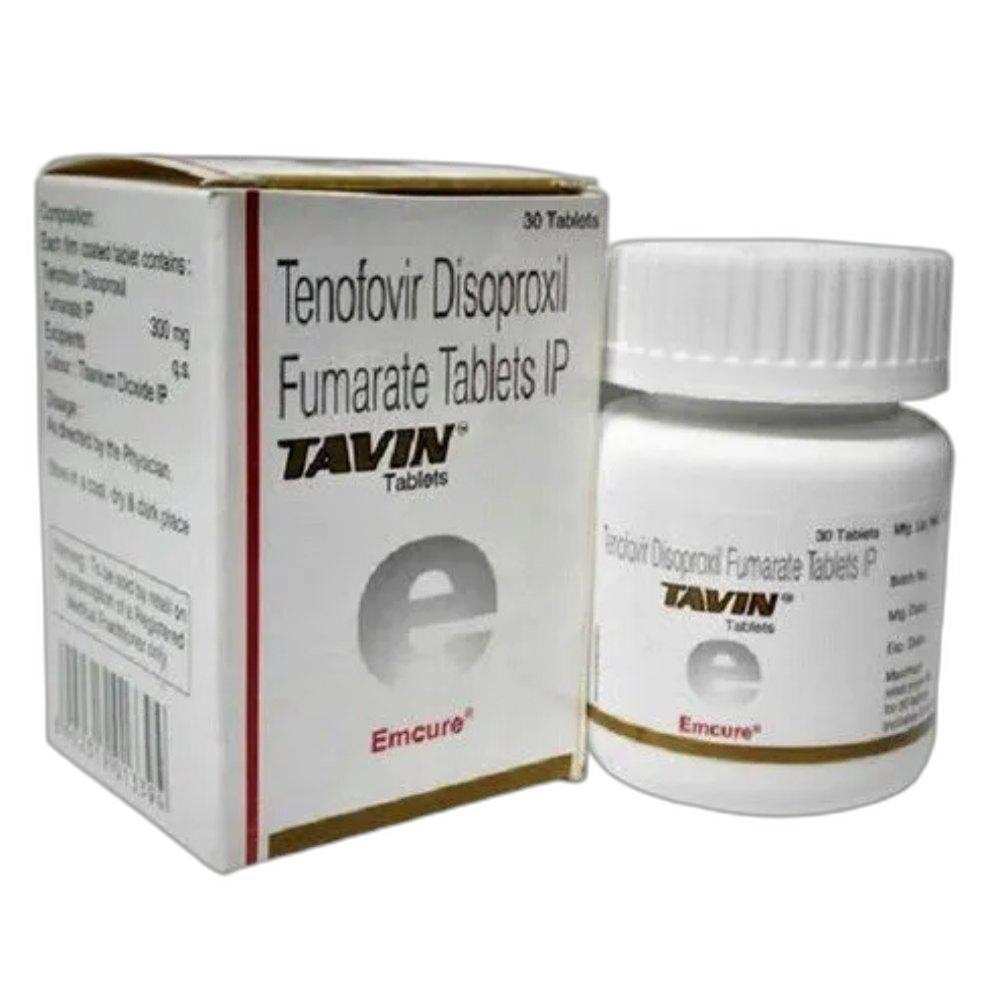
Hobart's Royal Hobart Hospital infectious disease unit serves Tasmania's small but geographically dispersed HIV and Hepatitis B patient population — including patients from regional Tasmania (Launceston, Devonport, Burnie) who travel to Hobart for specialist HIV and hepatology care. Tasmania's island isolation and limited specialist resources mean medication supply continuity is particularly critical. Tavin TDF 300mg provides Hobart patients with affordable, reliable antiviral supply at dramatically reduced cost.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: What are the unique challenges of managing HIV and Hepatitis B in Tasmania's geographically dispersed population?
Tasmania's geographic isolation — an island state with approximately 550,000 people spread across 68,000 square kilometres — creates distinctive healthcare access challenges for HIV and HBV patients. Specialist HIV and hepatology services are concentrated at Royal Hobart Hospital, with limited outreach to regional areas. Patients from Launceston (2 hours north), Devonport (3 hours), and Queenstown (3+ hours through mountain roads) face substantial travel burdens for clinic appointments. Tasmania's ferry crossing to mainland Australia creates an additional barrier for emergency medical supply situations. The small size of Tasmania's HIV-positive population — estimated below 500 individuals — means peer support networks are thin and anonymity concerns are acute (knowing one person in the clinic waiting room who knows your family compounds stigma-related treatment avoidance). Tavin's once-daily simplicity supports self-management between infrequent Hobart clinic visits, and Unnati Pharmax's reliable delivery to Hobart addresses the supply security concern that Tasmania's island geography amplifies. Telemedicine expansion from Royal Hobart Hospital to regional Tasmanian patients has partially addressed the access barrier, but medication supply remains a distinct challenge requiring reliable solutions like Unnati Pharmax.
FAQ 2: How does TDF (Tavin) treat Hepatitis B in Aboriginal Tasmanians — a population with specific health needs?Tasmania's Aboriginal Tasmanian (Palawa) community has specific health needs shaped by the devastating history of near-genocide, dispossession, and ongoing systemic disadvantage. While national HBV data for Aboriginal Tasmanians is limited, Tasmania's Tasmanian Aboriginal Centre and the broader Aboriginal Community Controlled Health Organisation (ACCHO) sector provide culturally safe primary care that includes HBV testing and management. HBV in Aboriginal Tasmanian communities — where rates of chronic liver disease from multiple causes including alcohol are elevated — carries particular risk of accelerated fibrosis progression and HCC risk. TDF (Tavin) for HBV treatment supports the long-term viral suppression needed to arrest fibrosis progression and prevent HCC in this community. Cultural safety — care delivered by Aboriginal health workers with community trust — is as important as the medication itself for treatment engagement and adherence in Aboriginal Tasmanian communities. Hobart's Tasmanian Aboriginal Centre works alongside Royal Hobart Hospital's hepatology team to provide integrated, culturally informed HBV management that includes medication support, dietary counselling, and alcohol harm reduction alongside Tavin prescribing.
FAQ 3: What is the PBS listing for Tavin in Australia and how does it compare to Tafsure for Hobart's HBV patients?Both TDF (Tavin, brand Viread) and TAF (Tafsure, brand Vemlidy) are PBS-listed in Australia for chronic Hepatitis B treatment — eligible Medicare cardholders receive both at PBS co-payment rates (approximately AUD $30 for general patients, free for concession). The clinical choice between TDF and TAF for Hobart's HBV patients is made by the prescribing hepatologist based on individual patient characteristics. TDF (Tavin) is preferred when: cost is the primary consideration and renal/bone profile is adequate; the patient is younger with normal kidney function and bone density; TAF is not yet formulary-listed at the prescribing institution. TAF (Tafsure) is preferred when: the patient has impaired kidney function; has osteoporosis or significant bone density reduction on DEXA; is older (above 60) where cumulative renal and bone effects become clinically important; or is a postmenopausal woman. For Hobart patients without PBS access (international visitors, temporary visa holders), Tavin from Unnati Pharmax at dramatically reduced cost addresses the full private pricing barrier — making a choice between TDF and TAF accessible based on clinical need rather than cost constraint.
FAQ 4: How does Hobart's cold, damp climate affect HBV patients' liver health and Tavin treatment?Hobart's subantarctic-influenced climate — cold winters, high rainfall, and limited sunshine particularly from May-August — creates specific contextual factors for HBV liver patients. Vitamin D deficiency is extremely common in Hobart's winter — the city's southern latitude and minimal winter sunshine hours mean many residents develop significant vitamin D insufficiency from June-August. Vitamin D deficiency has emerging evidence of association with accelerated hepatic fibrosis in chronic liver disease including HBV — making vitamin D supplementation clinically important for Hobart's HBV patients on Tavin. Additionally, TDF (Tavin) causes mild bone density reduction through phosphate-wasting mechanisms — and bone health is further threatened by vitamin D deficiency, making the combination of TDF use + Hobart's winter vitamin D insufficiency + Tasmania's relatively older HBV patient population a specific clinical consideration. Hobart's hepatologists routinely check vitamin D at HBV annual review and supplement 1,000-2,000 IU daily for deficient patients — complementing the calcium supplementation already recommended for TDF users. Seasonal affective disorder from Hobart's limited winter light also affects general wellbeing and indirect treatment adherence — a holistic consideration for the Royal Hobart Hospital hepatology team.
FAQ 5: What HBV surveillance for hepatocellular carcinoma (HCC) should Hobart patients on Tavin maintain and why?HCC surveillance for HBV patients on Tavin follows Australian liver disease guidelines — 6-monthly liver ultrasound ± AFP (alpha-fetoprotein) blood test for patients at elevated HCC risk. Who requires surveillance in Hobart's HBV population: all HBV-positive patients with cirrhosis (regardless of viral load status); Asian males over 40 and Asian females over 50 with chronic HBV (elevated HCC risk from ancestral HBV acquisition); African patients with HBV of any age; patients with family history of HCC; and patients with high HBV viral load history or ongoing replication despite treatment. The rationale for continued HCC surveillance even during effective Tavin viral suppression: the integrated HBV cccDNA in hepatocyte nuclei can drive oncogenic mutations even without active viral replication; cirrhotic liver architecture independently increases HCC risk regardless of the precipitating cause; and the carcinogenic effects of years of HBV-driven inflammation persist even after viral suppression. Hobart's Royal Hobart Hospital hepatology team coordinates HCC surveillance through the gastroenterology ultrasound service and gastroenterology outpatient clinic — a combined liver disease and HCC early detection programme that has improved HCC detection rates in Tasmania's HBV patients.