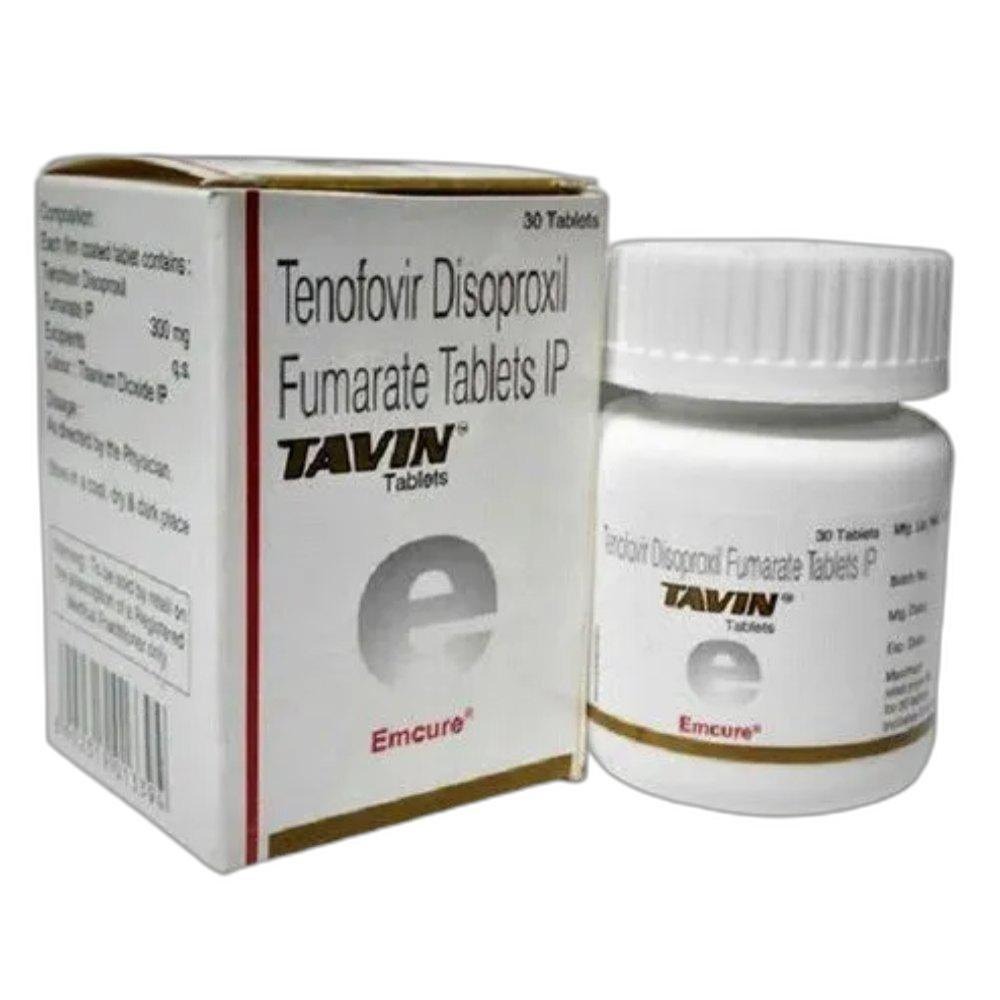
Adelaide's Royal Adelaide Hospital HIV and hepatology services manage South Australia's HIV-positive and chronic HBV population — including the state's International students without Medicare, temporary visa workers, and a diverse migrant community from Southeast Asia and the Pacific where HBV prevalence is elevated. Tavin TDF 300mg provides Adelaide patients requiring private antiviral supply with proven dual HIV/HBV efficacy at affordable cost versus brand Viread private pricing in SA.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
FAQ 1: How does TDF (Tavin) work differently in HIV versus HBV treatment — same drug, different diseases?Tenofovir Disoproxil Fumarate (Tavin) inhibits viral polymerase enzymes through the same chain-termination mechanism in both HIV and HBV — but the clinical application and treatment goals differ meaningfully between the two diseases. In HIV: Tavin is used as part of combination ART (never alone) — typically combined with Emtricitabine and a third agent; the goal is complete viral suppression (undetectable HIV RNA) enabling immune recovery and preventing AIDS progression; treatment is lifelong with no curative endpoint. In HBV: Tavin can be used as monotherapy or as part of combination regimens; the goal is HBV DNA suppression to undetectable levels, reducing liver inflammation and fibrosis risk; treatment is lifelong for most patients (indefinite suppression) with the exceptional endpoint of HBsAg loss (functional cure) occurring in 1-3% of treated patients per year of treatment; and dose and monitoring differ from HIV use. The elegant clinical advantage of Tavin's dual indication is most apparent in HIV/HBV co-infected patients — a single agent covers both viruses, simplifying the regimen while addressing both infections simultaneously. Adelaide's RAH infectious disease team routinely screens all HIV-positive patients for HBV co-infection at diagnosis specifically to identify this TDF dual-benefit scenario.
FAQ 2: How does the high HBV prevalence among Adelaide's Pacific Islander community affect Tavin prescribing?Pacific Islander communities — from Samoa, Tonga, Fiji, Papua New Guinea, and other Pacific nations — have among the world's highest HBV prevalence rates (8-20% in some island populations), reflecting high rates of perinatal and childhood horizontal transmission before universal vaccination was widespread. Adelaide has a growing Pacific Islander community, concentrated in southern suburbs like Morphett Vale and Christies Beach, working in healthcare, construction, and community services. Many Pacific Islander adults in Adelaide carry HBV acquired in childhood — often undiagnosed because HBV is frequently asymptomatic for decades. Adelaide's RAH hepatology team has conducted targeted HBV screening in Pacific Islander community health events — identifying previously undiagnosed HBsAg carriers who can then be assessed for Tavin treatment. Cultural considerations: Pacific Islander communities generally have strong family and church support structures that facilitate healthcare engagement; however, shame around liver disease associated with alcohol use (HBV has no alcohol connection, but stigma can be misdirected) occasionally creates disclosure barriers. Tavin's once-daily simplicity and excellent safety profile supports long-term adherence in Pacific Islander patients managing busy family and work lives in Adelaide's suburbs.
FAQ 3: What is the difference between Tavin (TDF) and Tafsure (TAF) specifically for Adelaide's older HBV patients?Adelaide's HBV patient population includes many patients in their 50s-70s who have been infected for decades — an age group where the bone and kidney safety differences between Tavin (TDF) and Tafsure (TAF) become clinically significant. For Adelaide patients over 60: cumulative bone density loss from TDF (averaging 2-3% at hip and spine over 2 years) adds to the normal age-related bone density decline that increases fracture risk — Tafsure's negligible bone effect is clinically meaningful for this age group; kidney function naturally declines at 0.5-1 mL/min per year after age 40 — TDF's mild additional renal tubular toxicity accelerates this in a population whose renal reserve is already diminishing; and diabetes (highly prevalent in Adelaide's older population, particularly from high-risk ethnic backgrounds) independently accelerates kidney disease, making TDF-induced tubular toxicity more clinically significant. Adelaide's RAH hepatology team typically initiates treatment with Tavin in younger patients where bone and kidney concerns are less immediate, while preferring Tafsure for patients over 60, those with established CKD (eGFR below 60), post-menopausal women, or those on corticosteroids — where TAF's safety advantages are most clinically valuable.
FAQ 4: Can Adelaide patients combine Tavin with alcohol consumption or does HBV change alcohol's liver impact?Alcohol and Tavin (TDF) do not have pharmacokinetic interactions — there is no direct drug-alcohol interaction that changes Tavin's blood levels or mechanism. However, alcohol's relationship with HBV-infected liver function is critically important. Alcohol causes hepatocellular injury through independent pathways from HBV — both conditions cause hepatocyte death and fibrosis through their own mechanisms. The combination accelerates fibrosis progression dramatically: HBV-infected patients who drink heavily have fibrosis progression 2-3 times faster than HBV patients who don't drink. Australian alcohol guidelines (no more than 10 standard drinks per week, no more than 4 on any single occasion) represent a maximum threshold even for healthy individuals — for Adelaide's HBV patients on Tavin, hepatology specialists recommend complete abstinence or minimal consumption to avoid compounding hepatic damage. Australia's culture of wine and beer — particularly prominent in Adelaide's wine-adjacent identity (Barossa, McLaren Vale proximity) — means alcohol counselling is a critical part of every HBV management consultation at Adelaide's RAH. Tavin can suppress HBV perfectly while concurrent alcohol consumption causes independent progressive liver damage that undermines the treatment goal.
FAQ 5: What HBV screening programmes exist in South Australia and how do they connect patients to Tavin treatment?South Australia's HBV screening landscape includes several complementary pathways. Universal antenatal screening: all pregnant women in SA are screened for HBsAg — identifying HBV-positive mothers whose newborns receive immediate birth dose hepatitis B vaccine + HBIG immunoprophylaxis. GP-level screening: RACGP guidelines recommend screening all migrants from countries with HBV prevalence above 2% (covering most of Asia, Pacific, parts of Africa and Middle East) at their first GP encounter. Community health events: SA Health and SHINE SA run community HBV testing days in Pacific Islander, Vietnamese, Chinese, and Korean community centres in Adelaide's southern suburbs. Needle and syringe programmes: SA's NSP services screen for HBV in their client population given elevated prevalence in injecting drug users. Aboriginal Community Controlled Health Organisations in SA screen Aboriginal patients for HBV given higher prevalence. Once identified through any pathway, HBsAg-positive Adelaide patients are referred to RAH hepatology for FibroScan-guided assessment of whether Tavin treatment is indicated — completing the screening-to-treatment cascade that SA Health's HBV elimination strategy requires.