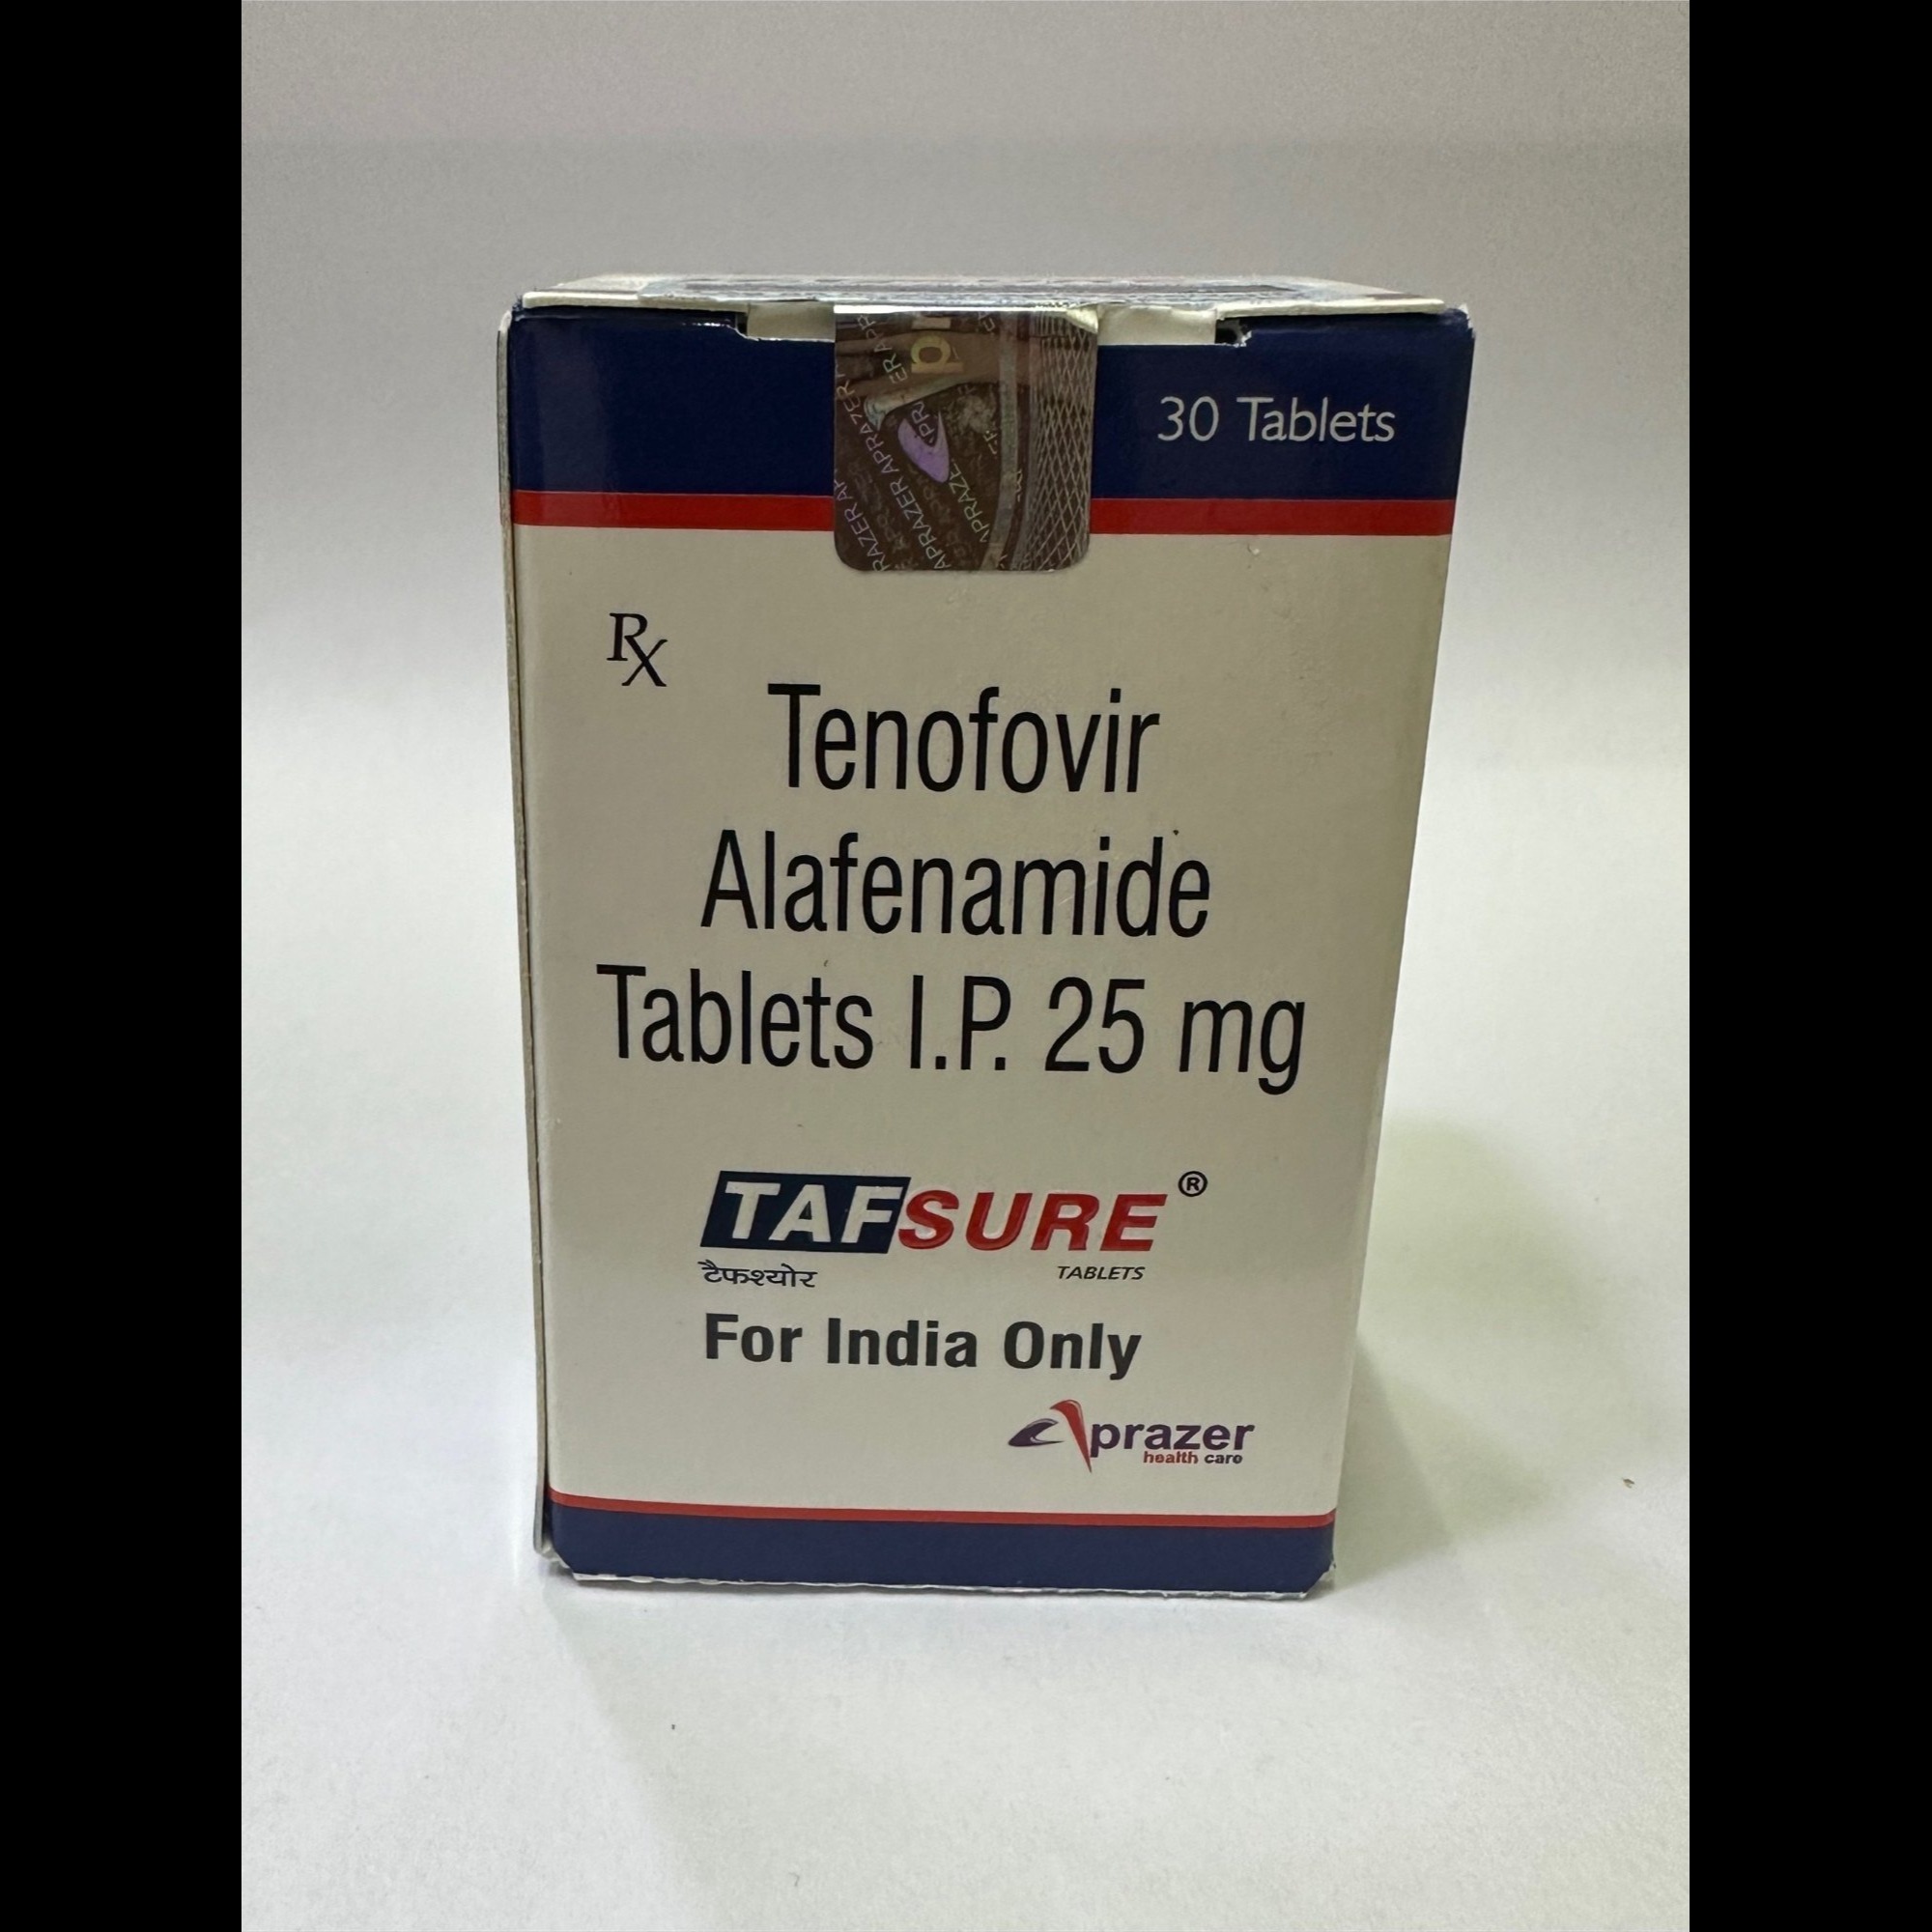
Minneapolis hosts one of America's largest Somali, Hmong, and East African immigrant communities — populations from countries with among the world's highest Hepatitis B prevalence rates. Hennepin Healthcare and University of Minnesota Medical Center hepatology services manage one of the Midwest's most diverse HBV patient populations. Tafsure TAF 25mg provides Minneapolis's immigrant HBV community with the most advanced, safest HBV suppression at dramatically reduced cost versus brand Vemlidy Minnesota retail pricing.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: Why do Minneapolis's Somali and Hmong communities have disproportionately high Hepatitis B rates and how does Tafsure address this?
Minneapolis's Somali community — one of America's largest, primarily resettled from refugee camps in Kenya and Ethiopia — carries HBV prevalence rates of 5-10% (compared to less than 1% in the US general population), reflecting Somalia's high endemic HBV burden where most transmission occurs perinatally or in early childhood before universal vaccination. Similarly, Minneapolis's Hmong community from Laos and Thailand carries HBV prevalence of 8-15% — Laos has among Southeast Asia's highest chronic HBV rates. Both communities arrived before their countries of origin implemented universal HBV vaccination programmes, meaning many adults were infected in childhood without vaccination protection. Cultural barriers to HBV screening and treatment in both communities include: language access (Somali and Hmong language medical resources are limited); limited familiarity with the US healthcare system; stigma in communities where HBV is sometimes associated with intravenous drug use (inaccurate for most community members infected perinatally); and historical trauma affecting healthcare trust. Tafsure's once-daily simplicity and minimal side effect profile support treatment adherence in these communities, while community health workers from Minneapolis's Somali and Hmong health organisations provide culturally and linguistically appropriate treatment navigation support.
FAQ 2: How does TAF (Tafsure) handle HBV suppression in Minneapolis patients with concurrent kidney disease from chronic conditions?Minneapolis's East African and Southeast Asian HBV-positive communities have elevated rates of chronic kidney disease — driven by diabetes (Type 2 diabetes prevalence is significantly higher in Somali and Hmong communities due to genetic factors, dietary transition, and physical inactivity from sedentary US lifestyle after physically active refugee camp and rural Asian village life), hypertension, and in some Hmong patients, specific inherited nephropathies. TAF (Tafsure) is specifically preferred over TDF (Tavin) for HBV patients with kidney disease because TAF delivers 89% lower plasma Tenofovir concentrations while maintaining equivalent intrahepatic drug levels — essentially eliminating the renal tubular toxicity that would accelerate kidney decline in already-CKD patients. Minneapolis's Hennepin Healthcare's combined hepatology-nephrology care model specifically positions TAF as the HBV treatment of choice for their kidney-compromised immigrant patients — with no dose adjustment required until eGFR falls below 15 mL/min (dialysis level). Tafsure's kidney-friendly profile makes it the right choice for the real-world comorbidity profile of Minneapolis's HBV-affected immigrant communities.
FAQ 3: What HBV vaccination programme should Minneapolis healthcare providers offer to unvaccinated family members of Tafsure users?HBV is efficiently transmitted within households — particularly through shared personal care items (razors, toothbrushes, nail clippers) and through childhood household contact. When a Minneapolis Tafsure user is diagnosed with chronic HBV, their entire household should be assessed for HBV vaccination status and immunity. Standard Minneapolis HBV household contact management: test all household members and close contacts for HBsAg (current infection), anti-HBs (immune from vaccination or prior infection), and anti-HBc (prior exposure marker). Vaccinate all susceptible individuals (HBsAg negative, anti-HBs negative) with the 3-dose HBV vaccine series — 0, 1, and 6 months. In Minnesota, HBV vaccination is universally recommended for all adults under 60 and for adults 60+ who are at increased risk (household contacts of HBV-positive individuals). Post-vaccination serology at 4-8 weeks after the third dose confirms protective anti-HBs levels (above 10 mIU/mL). Non-responders receive a repeat series. Minneapolis's Hennepin County Public Health provides HBV vaccination at no cost for uninsured household contacts of HBV-positive patients — an important resource for Minneapolis's immigrant communities where insurance coverage gaps are common.
FAQ 4: How does the Minnesota medical assistance (Medicaid) programme cover Tafsure for Minneapolis's low-income HBV community?Minnesota expanded Medicaid under the ACA — a decision that dramatically improved healthcare access for Minneapolis's low-income immigrant communities compared to non-expansion states. Minnesota Medical Assistance (MA) covers TAF (Vemlidy/Tafsure) for eligible HBV patients — including low-income adults, refugees (who qualify for MA during their initial resettlement period), and undocumented immigrants for emergency services (though not routine HBV treatment). Coverage gaps exist for: newly arrived immigrants in the waiting period before MA eligibility; those with income just above MA thresholds and insufficient for marketplace plans; and individuals who for complex immigration status reasons don't qualify for public coverage. For Minneapolis's HBV-positive immigrants in these coverage gaps, Tafsure from Unnati Pharmax provides affordable TAF-based HBV suppression at dramatically reduced cost versus full private pricing — preventing the treatment interruptions that cause HBV reactivation flares and liver disease progression during coverage transitions. Minnesota's HealthConnect navigation programme and Refugee Health Screener programme help connect newly arrived refugees to healthcare coverage and clinical services including HBV management.
FAQ 5: What is the risk of HBV reactivation in Minneapolis patients who stop Tafsure for non-medical reasons and how is it managed?HBV reactivation after stopping TAF (Tafsure) is a serious clinical risk that Minneapolis hepatologists communicate clearly to all patients initiating long-term HBV suppression. Unlike HCV (which can be permanently cured), HBV establishes a nuclear cccDNA reservoir in hepatocytes that persists indefinitely regardless of treatment — stopping Tafsure does not eliminate HBV but removes the suppression that was keeping replication at undetectable levels. Reactivation dynamics: after stopping Tafsure, HBV viral load typically rebounds within 4-12 weeks; in patients with established significant fibrosis or cirrhosis, reactivation can trigger severe or fulminant hepatitis with acute liver failure risk; even in non-cirrhotic patients, reactivation hepatitis can cause clinically significant acute-on-chronic liver disease. Management of unavoidable Tafsure interruption: if Tafsure must be stopped (cost crisis, supply interruption), Minneapolis hepatologists advise: close clinical monitoring with HBV DNA and liver function tests every 4-8 weeks during the interruption; immediate reinstatement of Tafsure when possible; and seeking emergency bridging through Minnesota's pharmaceutical assistance programmes or Unnati Pharmax's urgent supply channel if the interruption is cost-driven. Tafsure should never be stopped abruptly without a clinical management plan in place.