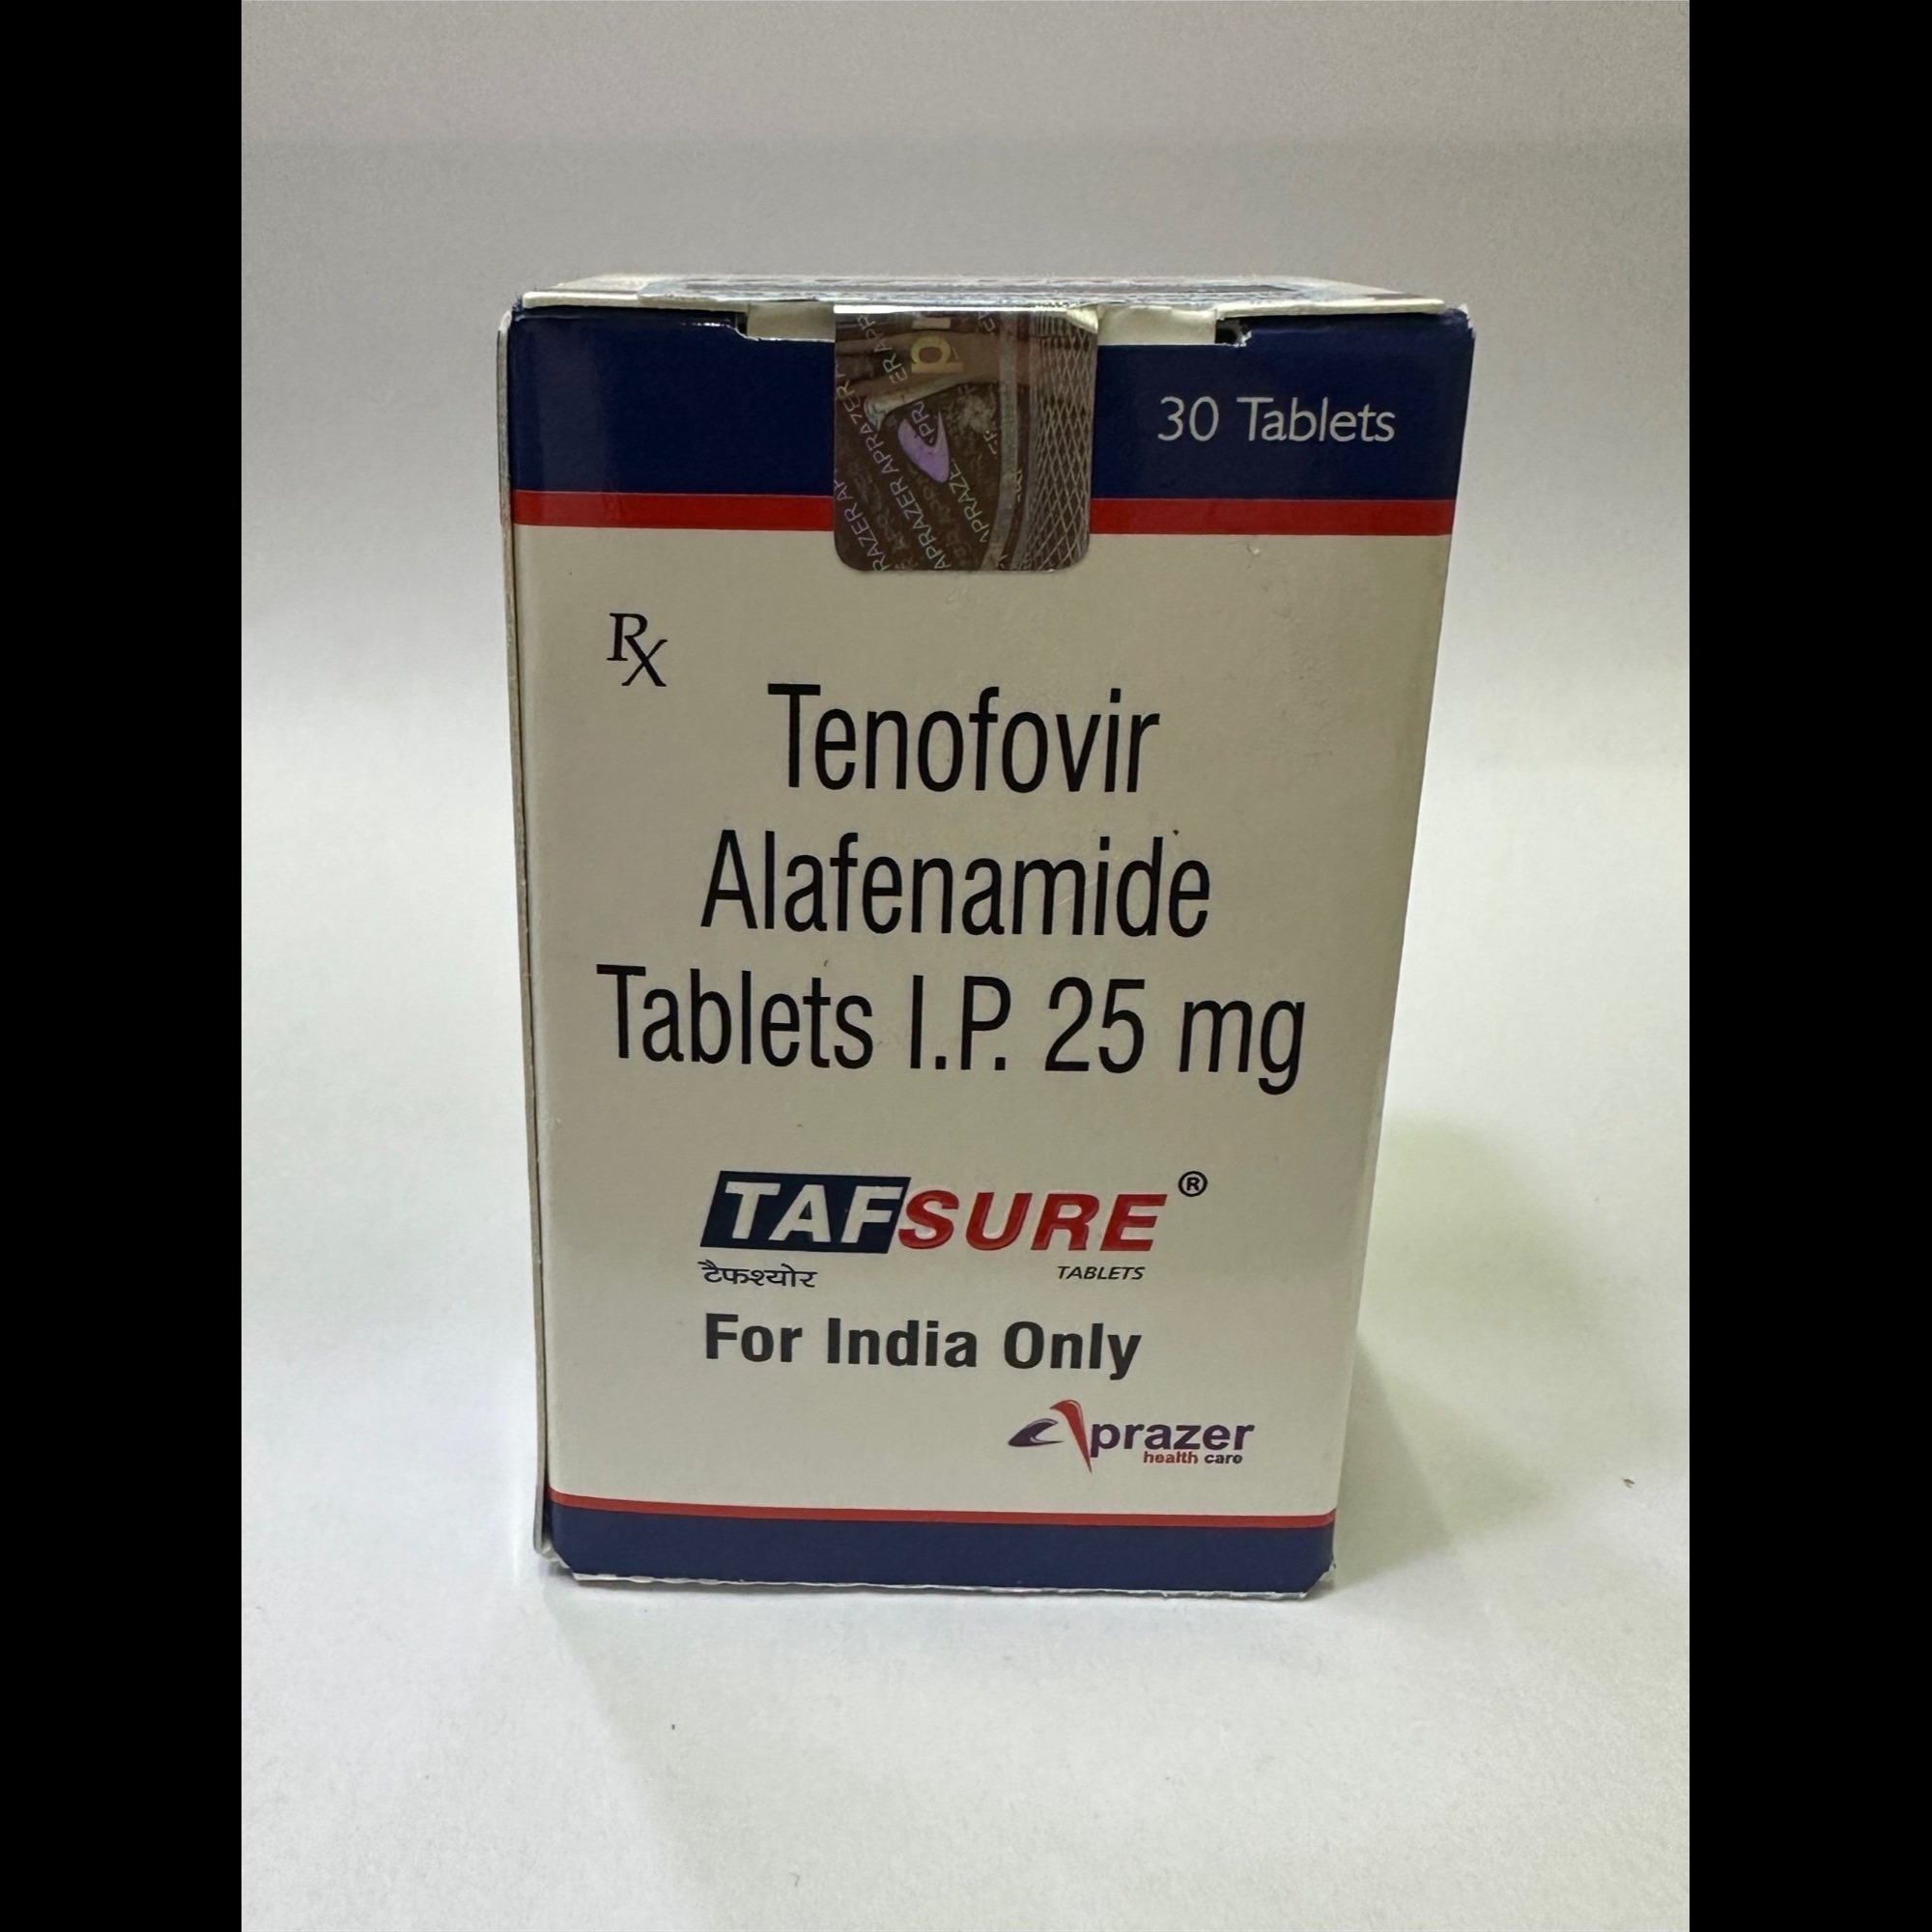
Abu Dhabi's large South Asian, East Asian, and Southeast Asian populations from HBV-endemic countries create substantial Hepatitis B treatment demand across the emirate's private healthcare network. For Abu Dhabi patients with chronic HBV outside insurance coverage for brand Vemlidy — or facing high co-payments — Tafsure provides the most advanced TAF-based HBV suppression at dramatically reduced cost through Unnati Pharmax with full WHO-GMP documentation.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
FAQ 1: How does the UAE's healthcare system handle HBV — is it covered for expat workers in Abu Dhabi?Abu Dhabi's mandatory health insurance framework (Daman, ADNIC, and other approved insurers) requires employers to provide basic health coverage for employees — but the scope of coverage for chronic conditions like HBV varies dramatically between plan tiers. Basic Abu Dhabi employer health plans — typically provided to lower-income South Asian and Southeast Asian workers — may cover acute medical care and essential medications but exclude or severely restrict coverage for specialty medications like antiviral therapy for chronic HBV. Enhanced plans for professional and managerial employees typically provide broader coverage including specialty medications, though prior authorisation is usually required for Vemlidy. UAE nationals receive coverage through SEHA (Abu Dhabi Health Services Company) that includes HBV antiviral treatment. The practical result: Abu Dhabi's construction workers, domestic employees, and lower-income service staff — precisely the population with highest HBV prevalence from high-prevalence South and Southeast Asian origin countries — are least likely to have insurance coverage for Tafsure. Unnati Pharmax's Tafsure provides these Abu Dhabi workers with affordable TAF-based HBV treatment that their insurance won't cover, preventing the liver disease progression that would otherwise occur from unaffordable treatment.
FAQ 2: How does HBV vaccination work in Abu Dhabi for newly arrived workers — can Tafsure substitute?Hepatitis B vaccination and Tafsure treatment serve completely different purposes and cannot substitute for each other. HBV vaccination: three-dose series creating protective antibodies (anti-HBs) in previously uninfected, HBsAg-negative individuals — prevents new HBV infection; highly effective (95%+ protection in immunocompetent adults); does not treat or affect existing HBV infection; Abu Dhabi's SEHA administers HBV vaccination at government health centres for UAE nationals and eligible expats. Tafsure treatment: for individuals ALREADY infected with HBV (HBsAg-positive) — suppresses viral replication, prevents liver damage progression, and reduces cancer and liver failure risk; has no preventive or protective role in uninfected individuals. The appropriate approach for newly arrived Abu Dhabi workers: test all new workers for HBsAg and anti-HBs; vaccinate HBsAg-negative, anti-HBs-negative workers (uninfected and unimmunised); link HBsAg-positive workers to Tafsure assessment and treatment. Abu Dhabi's occupational health screening programmes for large employers increasingly incorporate this dual HBV screening-and-vaccination/treatment approach — Tafsure serves the treatment arm of this programme
. FAQ 3: What is the natural history of HBV in Abu Dhabi's Filipino community and does it differ from Chinese or Pakistani patients?The Philippines, China, and Pakistan each have distinct HBV epidemiological profiles that affect the disease presentation in Abu Dhabi's respective communities. Filipino HBV: prevalence approximately 12-16% (among Southeast Asia's highest); predominantly perinatally acquired in generations before universal infant vaccination (introduced 1992 in Philippines); genotype B predominates — associated with higher rates of HBeAg seroconversion and potentially lower liver cancer risk than genotype C. Chinese HBV: prevalence 5-7%; genotype C predominates — associated with higher rates of severe chronic hepatitis, delayed HBeAg seroconversion, and higher HCC risk than genotype B; China's large population makes it the world's largest absolute HBV burden. Pakistani HBV: prevalence 3-5%; genotype D predominates — common in Central Asia and Middle East; may have different response characteristics to treatment and different natural history than Asian genotypes. These genotypic differences don't significantly affect Tafsure's treatment efficacy — TAF achieves excellent viral suppression across all HBV genotypes. However, they may affect baseline HCC surveillance intensity recommendations — genotype C Chinese patients warrant closer surveillance given their elevated HCC risk. Abu Dhabi's Sheikh Khalifa Medical City's hepatology team provides genotype-informed risk assessment for their diverse HBV patient population.
FAQ 4: How does Ramadan fasting affect Tafsure adherence for Abu Dhabi's Muslim HBV patients?Ramadan's daylight fasting creates medication adherence challenges that HBV specialists in Abu Dhabi specifically address in pre-Ramadan patient consultations. Tafsure (TAF 25mg) is a once-daily tablet — it can be taken with Suhoor (pre-dawn meal) or Iftar (sunset breaking of fast) without significant pharmacokinetic impact. Tafsure's absorption is not significantly affected by fasting state versus fed state — unlike some medications that are food-dependent for absorption. Practical Ramadan Tafsure management for Abu Dhabi's Muslim HBV patients: take Tafsure at Suhoor if the pre-dawn meal is a regular habit — morning dosing establishes a consistent routine; alternatively take at Iftar if Suhoor is skipped — the key is consistent timing at the same Ramadan meal each day; do not skip doses on fasting days — HBV viral replication can resume within days of Tafsure interruption, and the rebound flare risk is real especially when liver disease is more advanced. Abu Dhabi's SKMC hepatology team holds a pre-Ramadan HBV clinic specifically addressing medication management during fasting — recognising that culturally appropriate medication counselling improves adherence outcomes for Abu Dhabi's large Muslim HBV patient population.
FAQ 5: What is the long-term prognosis for Abu Dhabi's HBV patients on Tafsure — what can they realistically expect?Long-term prognosis for Abu Dhabi's HBV patients initiating Tafsure at various disease stages is generally excellent, though stage-dependent. For non-cirrhotic patients (F0-F2 fibrosis) starting Tafsure early: 95%+ achieve viral suppression within 48 weeks; liver inflammation resolves and fibrosis may actually regress over years; liver function normalises; HCC risk falls by 70-80% compared to untreated HBV; life expectancy approaches that of uninfected individuals with good treatment compliance; and HBsAg loss (functional cure) occurs in 1-3% per year — cumulative over decades of treatment, this means a meaningful proportion eventually achieve functional cure. For patients with established cirrhosis (F4): viral suppression prevents further fibrosis and decompensation; liver function typically stabilises and may improve modestly; HCC risk falls significantly but remains elevated above the non-cirrhotic population — surveillance ultrasound every 6 months is lifelong; liver transplant assessment remains appropriate if decompensation occurs despite treatment. For Abu Dhabi's working-age HBV patients in their 30s-50s initiating Tafsure now, a realistic expectation is several more decades of productive, healthy working life — with the liver damage stopped at its current stage and potentially partially reversed — provided treatment is maintained and alcohol avoidance and metabolic health are managed appropriately.