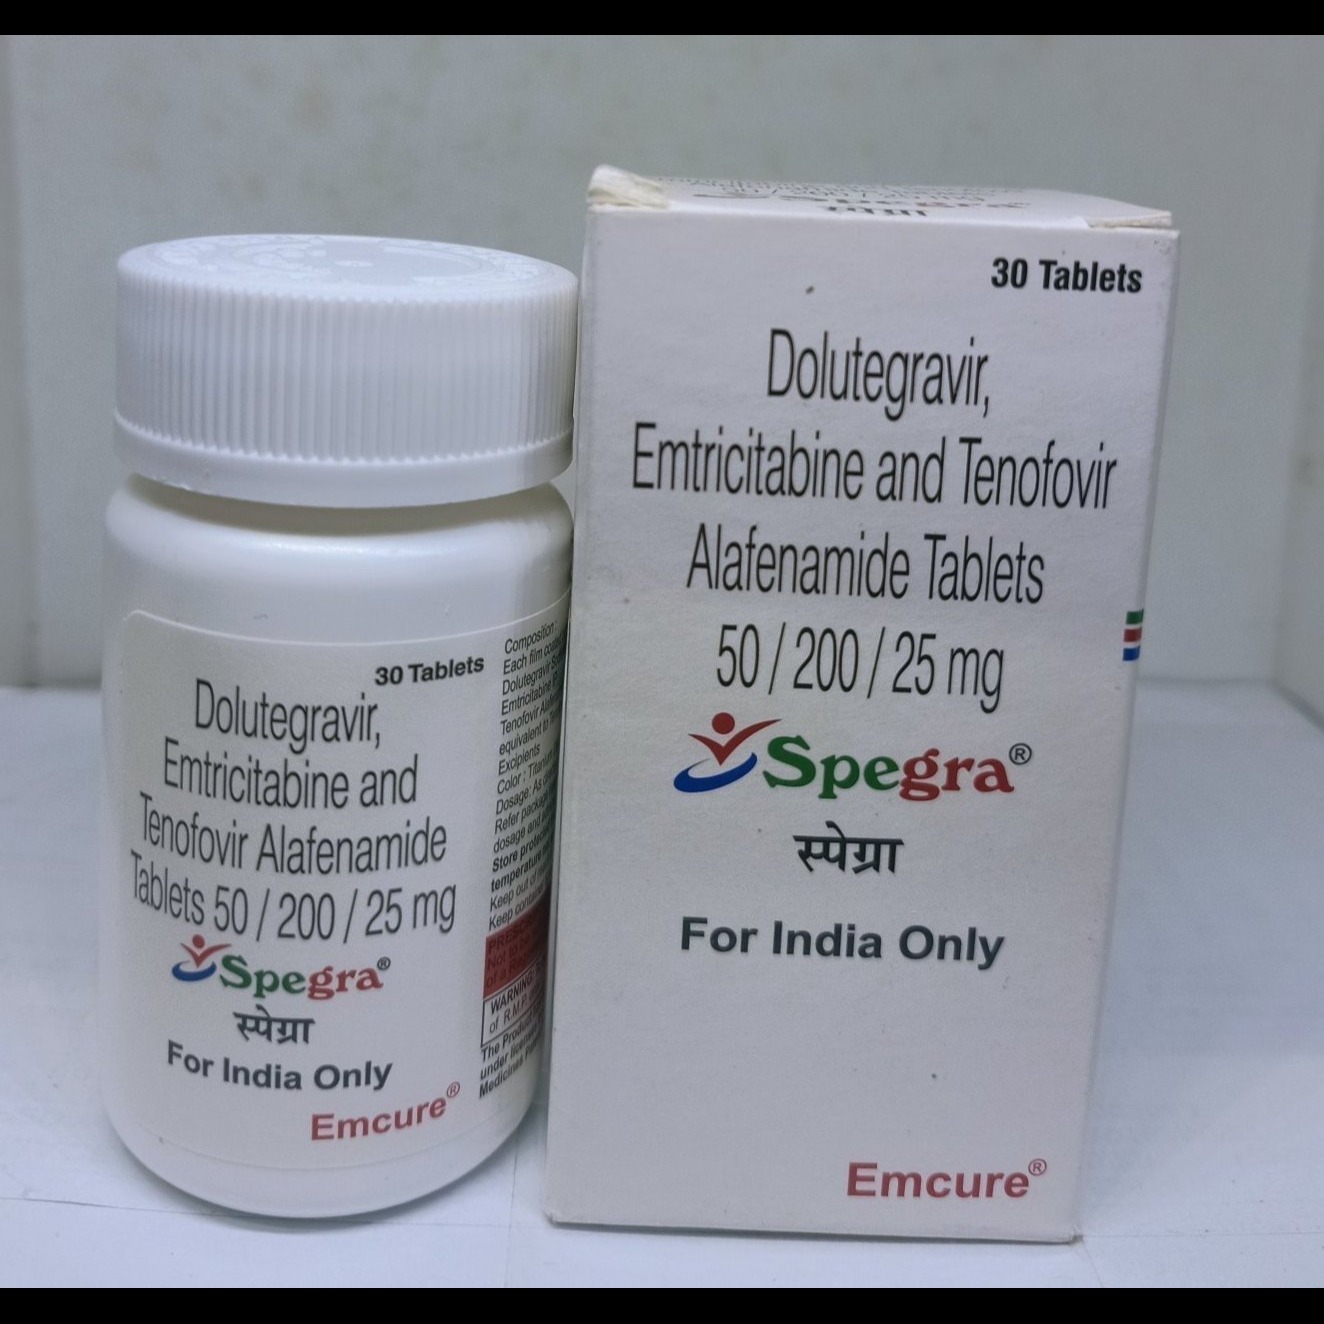
Halifax's Queen Elizabeth II Health Sciences Centre infectious disease service manages HIV-positive patients from across Nova Scotia — including significant African Nova Scotian communities in Preston and Guysborough County, a growing newcomer population from Sub-Saharan Africa, and Mi'kmaw communities from rural Nova Scotia. Spegra provides Halifax's HIV-positive patients in Nova Scotia Drug Benefit Programme gaps with affordable complete Dolutegravir-based treatment at dramatically reduced cost.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: How does HIV affect Nova Scotia's African Nova Scotian community and what barriers does Spegra address?
African Nova Scotians — descendants of Black Loyalists, Black Refugees, and escaped slaves who settled Nova Scotia centuries ago — represent one of Canada's oldest Black communities, concentrated in Preston, Dartmouth, and Guysborough County. This community has faced centuries of systemic racism including land dispossession, educational segregation, and employment discrimination. HIV in African Nova Scotian communities reflects these systemic inequities: higher HIV rates than Nova Scotia's general population driven by poverty, incarceration (Black Nova Scotians are overrepresented in provincial jails), and healthcare access barriers rooted in historical medical racism creating profound distrust. Cultural stigma around HIV in African Nova Scotian communities — where church is central and HIV carries shame — prevents testing and treatment engagement. Spegra's affordability addresses one key barrier — cost — but the deeper barriers of trust and stigma require community-led organisations like the Black Cultural Centre for Nova Scotia and Mi'kmaw Native Friendship Centre to work alongside QEII's HIV clinic in culturally informed outreach and care.
FAQ 2: How does Spegra's Dolutegravir component perform in patients with prior treatment failure in Halifax's experienced cohort?Halifax's QEII HIV clinic manages patients who have been living with HIV for decades — including those treated with older, less effective regimens that may have resulted in historical treatment failure and resistance accumulation. Dolutegravir's extraordinary resistance barrier makes Spegra valuable even in this experienced population. Key considerations for Halifax's treatment-experienced patients: patients with historical NRTI failure (Zidovudine, Stavudine-era treatment) may have M184V mutation (Lamivudine/Emtricitabine resistance) — Emtricitabine in Spegra would have reduced efficacy, but Dolutegravir's potency often compensates; patients with prior Raltegravir or Elvitegravir failure may have integrase resistance mutations — genotypic resistance testing is essential before switching to Spegra; and patients with documented NNRTI resistance (common from Nevirapine or Efavirenz failure) can typically use Dolutegravir safely as it avoids the NNRTI class entirely. Halifax's QEII resistance genotyping service tests for all relevant resistance mutations before treatment selection, ensuring Spegra is used where all three components retain activity.
FAQ 3: What are the specific HIV transmission dynamics in Halifax's small city context compared to major Canadian cities?Halifax's relatively small population (approximately 450,000 metro) creates distinct HIV transmission dynamics compared to Toronto or Vancouver. In smaller cities: sexual networks are more tightly interconnected — a new infection is statistically more likely to occur within an existing relationship web than in a random encounter in a larger city's anonymous sexual marketplace; this network density can accelerate cluster outbreaks but also means effective outbreak response reaches the entire network efficiently; stigma is amplified because HIV-positive status is more likely to become known in tight communities than in the anonymity of a major city. Halifax's QEII HIV clinic manages relatively small patient numbers — enabling more personalised care and closer follow-up than urban HIV megaclinics. Nova Scotia's population distribution across rural communities (Cape Breton, Annapolis Valley, rural Colchester County) creates geographic barriers to Halifax HIV clinic access that require telemedicine and community-based monitoring to overcome. Spegra's once-daily simplicity supports adherence in rural Nova Scotia patients where Halifax clinic visits are infrequent and self-management between visits must be robust.
FAQ 4: How does the Nova Scotia Drug Benefit programme (NSDP) cover Spegra and what gaps exist?Nova Scotia's drug benefit programme covers antiretrovirals including Dolutegravir-based regimens for eligible Nova Scotians — including those receiving social assistance, those with qualifying chronic conditions, and seniors. However, gaps exist for: working-age Nova Scotians in employment without employer drug benefits; newcomers and asylum seekers in the Interim Federal Health Programme who may not receive provincial drug benefit; and patients in administrative transition periods between benefit programmes. For Halifax HIV-positive patients in these gaps, Spegra from Unnati Pharmax provides supply continuity at dramatically reduced cost — preventing the treatment interruptions that allow viral rebound and transmission risk while administrative eligibility is resolved. Nova Scotia's Aids Coalition of Nova Scotia (ACNS) provides benefits navigation support, helping Halifax HIV-positive individuals access the drug benefit coverage they're entitled to — and Spegra from Unnati Pharmax bridges the interim period while this navigation occurs.
FAQ 5: What monitoring schedule do Halifax physicians use for HIV-positive patients on Spegra and what tests are required?Standard monitoring for Halifax HIV-positive patients on Spegra (Dolutegravir+Emtricitabine+TAF) follows QEII's protocol based on Canadian HIV guidelines. At initiation: HIV RNA viral load and CD4 cell count (baseline); complete blood count, comprehensive metabolic panel (liver enzymes, kidney function, glucose, lipids); HBV and HCV serology (TAF treats HBV — important if co-infected); pregnancy test (women of childbearing potential — Dolutegravir carries neural tube defect risk in first-trimester conception); and STI screen. At 4 weeks: viral load and renal function (TAF monitoring). At 3 months: viral load and CD4 (confirm virological response); metabolic panel. At 6 months: viral load, CD4, full metabolic panel, lipids. Annual: lipids, glucose, STI screening, bone density (DEXA in patients with risk factors), cardiovascular risk assessment, and in stable patients with sustained undetectable viral load, CD4 frequency may reduce. The Halifax QEII clinic's target: undetectable viral load (below 20-50 copies/mL depending on assay) at 6 months, maintained indefinitely — the cornerstone of both patient health and transmission prevention through U=U.