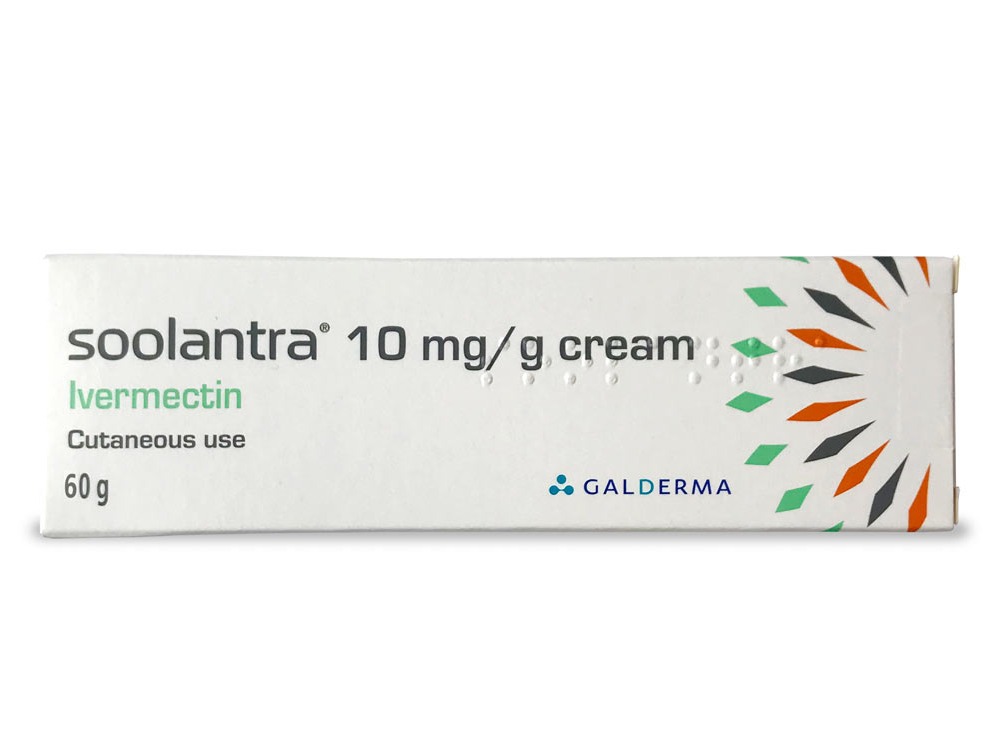
London's predominantly fair-skinned, Celtic and Northern European heritage population has among the UK's highest rosacea prevalence — a chronic inflammatory skin condition causing persistent facial redness, visible blood vessels, and papulopustular eruptions. Soolantra 1% (Ivermectin cream) is the most advanced rosacea treatment, targeting the Demodex mite component alongside inflammatory pathways. Unnati Pharmax delivers Soolantra to London at dramatically reduced cost versus UK brand pricing of £60-80 per tube.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: What is the Demodex mite hypothesis of rosacea and how does Ivermectin in Soolantra target it?
Demodex folliculorum — a microscopic mite that inhabits facial hair follicles — is present on virtually all adult human skin in small numbers. In rosacea patients, Demodex density is significantly elevated (10-18 times higher than in non-rosacea skin), and this overcolonisation triggers an aberrant immune response. Demodex mites carry bacteria (Bacillus oleronius) on their surface, and when mites die and release their bacterial load into follicles, this triggers toll-like receptor (TLR) 2-mediated inflammatory cascades that drive rosacea's papulopustular component. Ivermectin (Soolantra) kills Demodex mites through glutamate-gated chloride channel inhibition — selectively toxic to invertebrates including mites while safe for human skin cells. Additionally, Ivermectin has direct anti-inflammatory properties independent of its acaricidal action — inhibiting cytokine production and reducing the inflammatory cascade. London dermatologists at UCLH and St John's Institute use Soolantra specifically for papulopustular rosacea where Demodex overgrowth is the dominant pathogenic mechanism.
FAQ 2: How does Soolantra 1% compare to Metronidazole gel (Rozex) for rosacea treatment in London?Both Soolantra (Ivermectin 1%) and Rozex/Metrogel (Metronidazole 0.75-1%) are topical rosacea treatments, but they work through different mechanisms and have different evidence profiles. Head-to-head clinical trials directly comparing Ivermectin 1% versus Metronidazole 0.75% — including the landmark ATTRACT study — consistently show Ivermectin's superiority: greater reduction in inflammatory lesion count (41% greater lesion reduction at 52 weeks), better patient-reported outcomes, and higher rates of treatment success. Ivermectin's dual mechanism (Demodex kill + anti-inflammatory) versus Metronidazole's primarily anti-inflammatory action explains this superiority. For London patients previously treated with Metronidazole who have achieved partial but unsatisfactory control, switching to Soolantra typically produces additional significant improvement. London dermatologists now position Ivermectin as first-line for papulopustular rosacea in most clinical guidelines, with Metronidazole reserved as second-line or for patients who find Soolantra's cost prohibitive — where Unnati Pharmax's pricing makes Soolantra the cost-accessible first choice.
FAQ 3: What dietary triggers worsen rosacea in London's population and how should Soolantra users manage them?Rosacea has well-documented dietary triggers that London patients must manage alongside Soolantra treatment — medication treats the inflammatory and Demodex component, but triggers accelerate flushing and redness independently. Common rosacea dietary triggers: alcohol (particularly red wine and spirits — vasodilatory effect causing flushing; highly relevant for London's pub and wine culture); hot beverages (coffee and tea at high temperature — thermal vasodilation; London's tea culture makes this practically important); spicy food (capsaicin activates TRPV1 receptors causing neurogenic flushing; relevant for London's curry houses and South Asian restaurant culture); and dairy products in some patients. The National Rosacea Society recommends a trigger diary — London patients on Soolantra identify their personal triggers (which vary between individuals) by systematic elimination and reintroduction. Managing triggers reduces flushing frequency and severity, allowing Soolantra's anti-inflammatory effect to produce more visible improvement on a lower inflammatory baseline.
FAQ 4: Can Soolantra 1% be used for rosacea affecting the eyes (ocular rosacea) in London patients?Ocular rosacea — affecting the eyelids and ocular surface — occurs in approximately 50-60% of rosacea patients, causing blepharitis (eyelid inflammation), meibomian gland dysfunction, conjunctival injection, and in severe cases corneal involvement. Soolantra 1% cream is specifically licensed for facial use and must not be applied directly to the eyes or eyelid margins. However, evidence suggests that treating facial rosacea effectively with Soolantra reduces the inflammatory load that contributes to ocular involvement — some studies show facial Ivermectin treatment improves ocular rosacea symptoms through the reduction in systemic inflammatory mediators. Dedicated ocular rosacea treatment requires ophthalmology or specialist optometrist involvement: warm compresses and eyelid hygiene; oral Doxycycline (which reduces meibomian gland inflammation systemically); topical Cyclosporine eye drops for dry eye component; and in severe corneal involvement, specialist corneal management. London patients with both facial and ocular rosacea benefit from coordinated dermatology and ophthalmology care at centres like Moorfields Eye Hospital alongside Soolantra for their facial component.
FAQ 5: How does London's climate affect rosacea severity and Soolantra treatment outcomes?London's climate — characterised by cold, damp winters, mild summers, and frequent temperature changes — interacts significantly with rosacea. Cold wind and sudden temperature transitions (moving between heated interiors and cold exteriors) trigger neurogenic vasodilation that worsens facial flushing and erythema — a particular challenge for London's commuting population transitioning between underground tube heat and winter cold. Central heating in London's older housing stock creates very dry indoor air that worsens skin barrier dysfunction in rosacea. Summer UV exposure (even London's modest UV) worsens rosacea inflammation — broad-spectrum SPF 30-50 is essential year-round, using mineral rather than chemical sunscreens (more tolerated on rosacea-sensitive skin). Soolantra's effectiveness on London's rosacea patients is therefore best realised when complemented by climate management: protective face coverings in cold wind, indoor humidification, gentle mineral SPF, and trigger avoidance. London dermatologists at King's College Hospital rosacea clinic provide comprehensive seasonal management advice alongside Soolantra prescribing — recognising that London's specific climate pattern requires tailored rosacea management beyond medication alone.