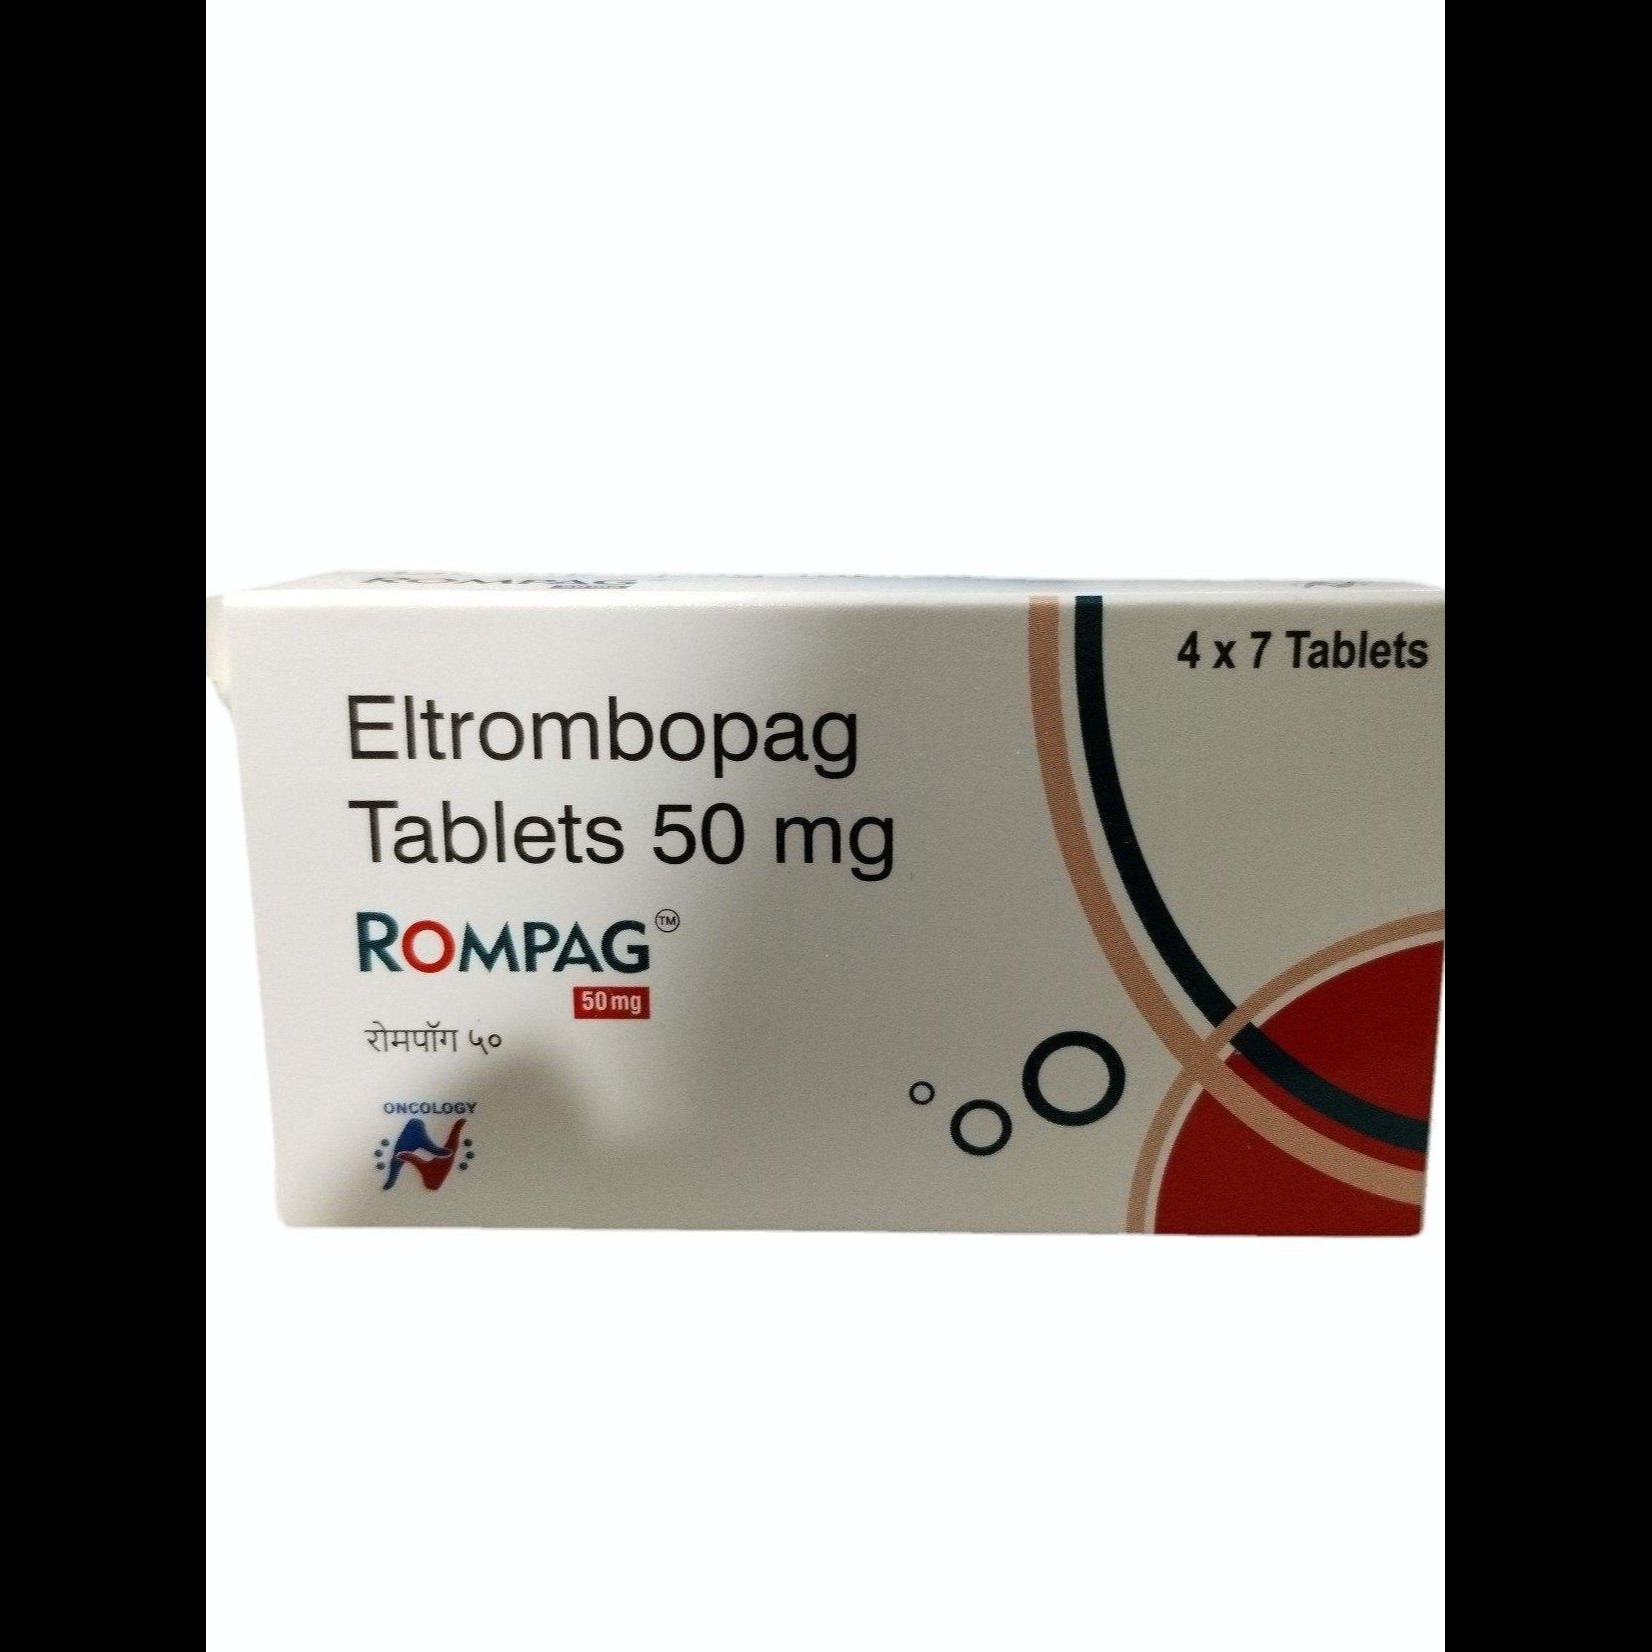
Los Angeles's Cedars-Sinai Medical Center, USC Norris Cancer Center, and UCLA Haematology manage severe aplastic anaemia and refractory ITP patients requiring dose-escalated Eltrombopag from across Southern California. LA's vast, diverse population — with the largest Mexican-origin community in the US, significant Asian and African American communities — creates distinct aplastic anaemia and ITP presentations. Rompag 50mg provides LA patients with high-dose Eltrombopag at dramatically reduced cost versus brand Revolade California retail pricing.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: How does aplastic anaemia present differently in LA's Latino community and what drives higher severity?
Aplastic anaemia — bone marrow failure causing pancytopenia — has important demographic patterns in Los Angeles's diverse population. Latino communities in LA have historically had higher exposure to benzene and other haematotoxic chemicals through agricultural work in the San Joaquin Valley and Central Valley regions that supply LA's food markets; pesticide and organic solvent exposure is an established aplastic anaemia risk factor. Some LA Mexican-origin patients present with aplastic anaemia linked to herbal medicine use — certain traditional Mexican herbal remedies (particularly some Inmortal plant preparations) have been associated with aplastic anaemia in case reports. Parvovirus B19 — which can cause aplastic crisis and in immunocompromised patients persistent marrow suppression — circulates in crowded LA communities and childcare settings. Hepatitis-associated aplastic anaemia (where aplastic anaemia follows a seronegative hepatitis episode) is seen in LA's populations from regions with higher hepatitis exposure. LA's Cedars-Sinai and USC Norris haematologists assess for all these aetiology possibilities before confirming idiopathic aplastic anaemia and initiating Rompag 50mg-based therapy — because some secondary aplastic anaemia causes (like drug or toxin exposure) require removal of the causative agent as the primary treatment.
FAQ 2: What is the standard ATG + Rompag 50mg protocol for severe aplastic anaemia in LA's major medical centres?Severe aplastic anaemia (SAA) immunosuppression protocol at LA's Cedars-Sinai and UCLA — consistent with the landmark RACE trial data — follows a standard regimen: Horse ATG (h-ATG, Atgam) administered over 4 days at 40mg/kg/day as a continuous IV infusion with premedication (methylprednisolone + diphenhydramine); cyclosporine initiated on day 1 at 6mg/kg/day in two divided doses (targeting trough levels 200-400 ng/mL); Eltrombopag (Rompag 50mg — dose equivalent to 150mg total using three 50mg tablets daily) started on day 14 after ATG and continued for 6 months; and GCSF for severe neutropenia management. The trilineage response seen with this combination — ATG suppressing the immune attack on stem cells while Rompag stimulates haematopoietic stem cell recovery across all cell lineages — produces complete or partial haematological responses in 85-90% of SAA patients. Los Angeles haematologists note that responses typically become evident from 3-4 months — patients and families must be counselled on this timeline to prevent premature treatment abandonment during the waiting period when blood counts remain low despite effective therapy beginning.
FAQ 3: How does Rompag 50mg support aplastic anaemia patients between ATG and potential stem cell transplant in LA?For LA aplastic anaemia patients who are young (under 40) with a matched sibling donor, allogeneic stem cell transplant (allo-SCT) offers the best curative potential — 80-90% long-term survival with curative intent. However, donor identification, pre-transplant work-up, and transplant preparation take weeks to months. During this period, Rompag 50mg-based therapy serves as a critical bridge — maintaining adequate platelet and neutrophil counts to prevent life-threatening bleeding or infection while transplant proceeds. For patients without matched sibling donors, Rompag + ATG + cyclosporine is the primary treatment rather than a bridge — and the 85-90% response rate means many LA patients avoid transplant entirely. For patients who achieve haematological response to Rompag + ATG but subsequently relapse, unrelated donor (MUD) transplant becomes the preferred salvage — with Cedars-Sinai's bone marrow transplant programme performing MUD transplants for relapsed SAA. Rompag 50mg's continued role in these patients: maintaining adequate counts while MUD donor search proceeds through NMDP (National Marrow Donor Program), which LA haematologists initiate simultaneously with ATG treatment in all SAA patients without matched sibling donors.
FAQ 4: What is PNH (paroxysmal nocturnal haemoglobinuria) and how does it relate to Rompag 50mg therapy in LA?Paroxysmal nocturnal haemoglobinuria (PNH) is a clonal haematopoietic stem cell disorder caused by somatic mutations in the PIG-A gene — resulting in GPI-anchor protein deficiency on blood cell surfaces. PNH cells are uniquely susceptible to complement-mediated destruction, producing haemolytic anaemia, thrombosis, and marrow failure. PNH is closely related to aplastic anaemia — PNH clones are found in 50-60% of aplastic anaemia patients, and 15-20% of aplastic anaemia patients eventually develop clinically significant PNH. Rompag 50mg therapy for aplastic anaemia affects PNH clone dynamics: Eltrombopag stimulates haematopoietic stem cell recovery, but the proliferating cells may include PNH clones that are selected by the aplastic marrow environment. LA's Cedars-Sinai haematology monitors PNH clone size by flow cytometry every 6-12 months in aplastic anaemia patients on Rompag — expansion of PNH clones is common and not automatically concerning, but rapidly expanding clones with clinical haemolysis or thrombosis warrant PNH-specific treatment with complement inhibitors (Eculizumab, Ravulizumab). This PNH-aplastic anaemia intersection is an important monitoring component of the Rompag programme at LA's major haematology centres.
FAQ 5: What support organisations exist for LA aplastic anaemia patients on Rompag 50mg treatment?LA's aplastic anaemia patient community has access to specific national and local support resources. The Aplastic Anemia and MDS International Foundation (AAMDSIF) — the primary US patient organisation for aplastic anaemia, MDS, and PNH — provides: specialist nurse helpline staffed by haematology nurse practitioners familiar with Rompag and ATG protocols; comprehensive disease education materials; a national patient registry connecting LA patients with clinical trials at UCLA, Cedars-Sinai, and USC Norris; peer mentoring connecting newly diagnosed LA patients with experienced aplastic anaemia survivors; and annual patient education conferences. City of Hope — a comprehensive cancer centre in Duarte, serving LA's eastern suburbs — has an active blood and marrow transplant programme that includes aplastic anaemia management. Cedars-Sinai's haematology social work team provides LA patients with financial assistance navigation — particularly important for Rompag 50mg, where brand Revolade's cost can exceed $8,000-10,000 monthly without assistance. Novartis's Revolade patient assistance programme provides brand medication for eligible uninsured patients; for those with insurance gaps or who don't meet brand assistance criteria, Rompag 50mg from Unnati Pharmax provides a quality-certified affordable alternative that these LA support organisations can help patients navigate.