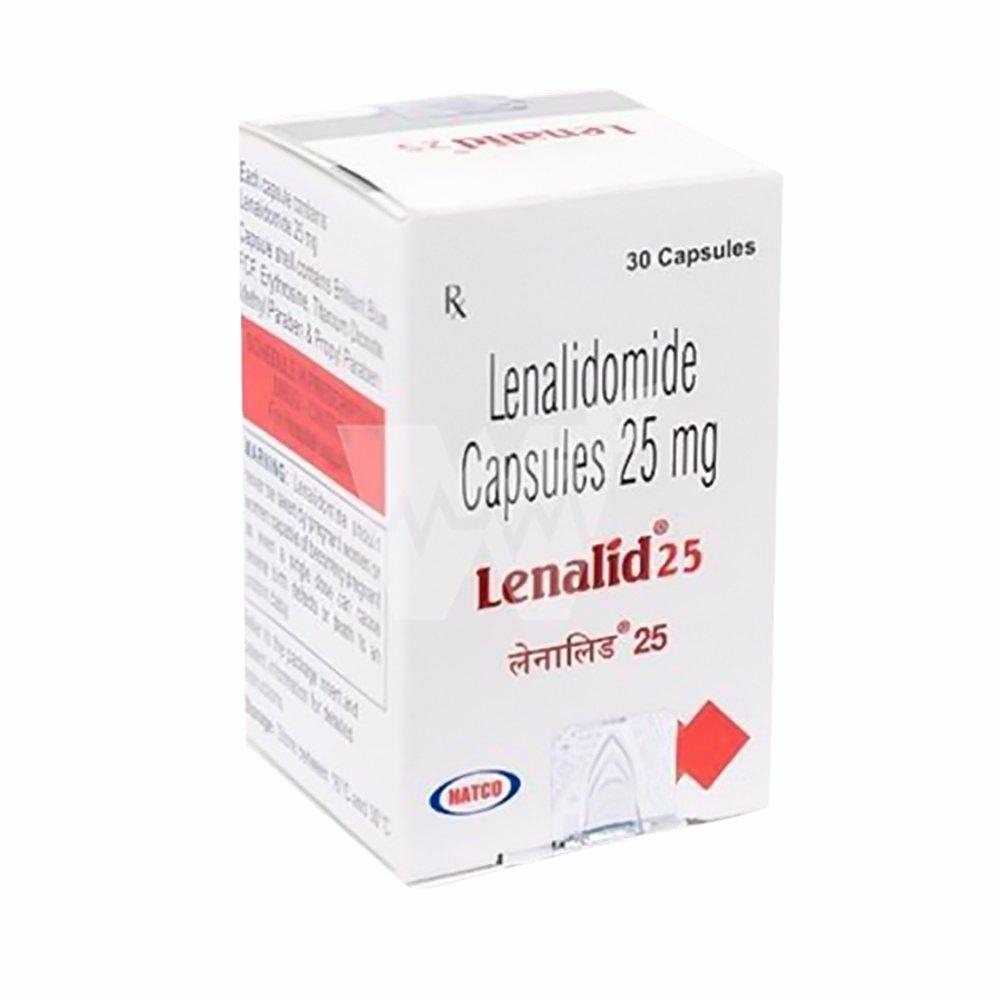
Gold Coast University Hospital haematology serves myeloma patients across the Tweed-Gold Coast region including the large retiree and lifestyle demographic that makes up a significant proportion of Queensland's southern coastal population. For Gold Coast myeloma patients outside PBS eligibility or self-funding treatment, Lenalid 25mg provides dramatically reduced cost access to this essential myeloma backbone therapy.
 FAQ 1: What is the mechanism of Lenalidomide's immunomodulatory effect in myeloma?
FAQ 2: What is the difference between Lenalid 25mg and 10mg, 15mg doses — when are lower doses used?
FAQ 3: What fatigue management strategies are available for Gold Coast myeloma patients on Lenalid?
FAQ 4: What is MYD88 mutation and how does it change treatment for lymphoplasmacytic lymphoma patients in Gold Coast?
FAQ 5: What sun protection and skin monitoring do Gold Coast myeloma patients on Lenalid need?
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
FAQ 1: What is the mechanism of Lenalidomide's immunomodulatory effect in myeloma?Lenalidomide (Lenalid) is classified as an IMiD (Immunomodulatory Drug) and works through a fascinating and complex mechanism centred on the CRBN (Cereblon) protein. Lenalidomide binds to Cereblon — a component of an E3 ubiquitin ligase complex — and changes the complex's substrate specificity, causing it to ubiquitinate (tag for destruction) two transcription factors: Ikaros (IKZF1) and Aiolos (IKZF3). In myeloma plasma cells, Ikaros and Aiolos are critical survival factors — their degradation drives myeloma cell death. Simultaneously, in normal T and NK cells, Ikaros and Aiolos degradation leads to T-cell activation and increased NK cell cytotoxicity — enhancing immune surveillance against myeloma. This dual mechanism — direct myeloma cell killing through cereblon-mediated transcription factor degradation, AND immune activation against residual myeloma — makes Lenalid unique among cancer drugs.
FAQ 2: What is the difference between Lenalid 25mg and 10mg, 15mg doses — when are lower doses used?Lenalidomide dosing is adjusted based on indication and renal function. For active myeloma treatment (induction and salvage), the standard dose is 25mg daily on days 1-21 of a 28-day cycle (21 days on, 7 days off). For post-transplant maintenance, lower doses of 10mg daily continuous (or 15mg for selected patients) are used — adequate for maintaining remission with better long-term tolerability. For non-transplant-eligible patients on continuous Rd (Lenalidomide + dexamethasone), 25mg continuous or cyclical dosing is standard. Dose reductions to 15mg, 10mg, or 5mg are made for haematological toxicity (low blood counts) or renal impairment — Gold Coast haematologists make these adjustments based on creatinine clearance (CrCl) and tolerance. Dose reductions do not eliminate efficacy — patients who achieve myeloma control at lower doses due to toxicity are generally maintained at those doses rather than re-escalating.
FAQ 3: What fatigue management strategies are available for Gold Coast myeloma patients on Lenalid?Cancer-related fatigue affects the majority of myeloma patients on Lenalidomide-based therapy and is one of the most impactful quality-of-life concerns. It arises from multiple sources: direct effects of Lenalidomide on energy metabolism, dexamethasone's disruption of sleep patterns (particularly if taken in the evening), anaemia from myeloma itself or myelosuppression, and the psychological burden of living with cancer. Evidence-based fatigue management for Gold Coast patients includes: structured aerobic exercise — the most robustly evidence-based intervention, even a 30-minute daily walk significantly reduces cancer fatigue; cognitive behavioural therapy specifically targeting cancer fatigue; optimising sleep hygiene and managing dexamethasone timing (morning administration reduces sleep disruption); treating contributory anaemia with EPO or transfusion if haemoglobin falls below 10g/dL; reviewing all medications for fatigue-inducing effects; and mindfulness-based stress reduction programmes available through Gold Coast University Hospital's cancer support services.
FAQ 4: What is MYD88 mutation and how does it change treatment for lymphoplasmacytic lymphoma patients in Gold Coast?MYD88 L265P mutation is present in approximately 90-95% of Waldenström's macroglobulinaemia (WM) — a lymphoplasmacytic lymphoma — and serves both diagnostic and therapeutic relevance. Diagnostically, detecting MYD88 L265P in a patient with monoclonal IgM paraproteinaemia strongly supports WM diagnosis. Therapeutically, the MYD88 L265P mutation activates BTK (Bruton's tyrosine kinase), making WM highly sensitive to BTK inhibitors like Ibrutinib. Gold Coast haematologists managing WM patients test MYD88 and CXCR4 mutation status, as CXCR4 mutations modify response to Ibrutinib. While Lenalidomide is occasionally used in WM, it is used less commonly than in myeloma due to different disease biology — BTK inhibitor-based regimens are preferred for most WM patients in current Australian practice. Understanding this distinction helps Gold Coast physicians direct the right therapy to myeloma versus WM diagnoses.
FAQ 5: What sun protection and skin monitoring do Gold Coast myeloma patients on Lenalid need?Lenalidomide (Lenalid) and other IMiDs are associated with increased skin toxicity including rash, and Gold Coast's intense UV environment creates specific risks for myeloma patients receiving immunomodulatory therapy. While Lenalidomide's direct skin effects (rash in 20-30% of patients, pruritus) are not UV-mediated, immunosuppression from corticosteroids in the regimen reduces the normal UV-protective immune surveillance that detects and destroys pre-malignant skin cells — increasing the risk of new skin cancers. Gold Coast's year-round high UV index makes formal dermatological monitoring particularly important: annual skin checks are recommended for all myeloma patients receiving prolonged immunosuppressive therapy, SPF 50+ sunscreen daily (not just on sunny days), protective clothing and hat when outdoors, and prompt review of any new or changing skin lesions. Gold Coast's cancer care teams routinely refer myeloma patients to dermatology for baseline assessment and annual surveillance.