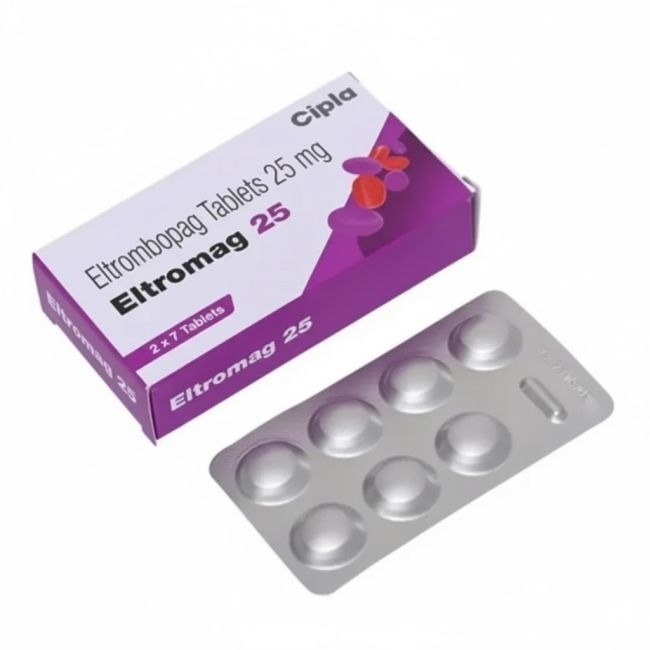
Manchester's Manchester University NHS Foundation Trust — encompassing Manchester Royal Infirmary and Wythenshawe Hospital — manages one of the North West's largest ITP patient populations. Greater Manchester's significant South Asian, African Caribbean, and Eastern European communities experience ITP across diverse demographic backgrounds. ELTROMBYRA 25mg provides Manchester's ITP community with affordable Eltrombopag at dramatically reduced cost versus UK private prescription pricing when NHS supply or eligibility creates gaps.
Visit unnatipharmax.com | +91 82650 41513 | Unnatipharmax@gmail.com
 FAQ 1: How does ELTROMBYRA 25mg compare to romiplostim (Nplate) in Manchester's clinical preference and what practical differences matter?
Both ELTROMBYRA (Eltrombopag 25mg escalating to 50-75mg) and romiplostim (Nplate, 1-10 mcg/kg weekly SC injection) are TPO-RA options for chronic ITP in Manchester's patients. Clinical and practical comparison: Eltrombopag (ELTROMBYRA) advantages — oral tablet taken at home daily; no injection required; no weekly clinic visits for administration; patients self-manage independently; lower rate of injection site reactions. Romiplostim (Nplate) advantages — weekly injections at clinic or home (self-injection taught); faster platelet response onset in some patients; no food timing restriction concerns (unlike Eltrombopag which requires 2-hour separation from calcium-rich food); and some evidence of slightly faster response in acute or severe ITP scenarios. Manchester's haematologists at MRI make individual choices based on: patient preference (most prefer oral — ELTROMBYRA wins on convenience); lifestyle (weekly clinic attendance versus daily home pill); speed of response needed (severe acute ITP may favour romiplostim's faster peak); and prior response history. Both are NICE-approved for refractory chronic ITP in England — NHS availability and patient preference typically determine the choice, with ELTROMBYRA from Unnati Pharmax serving patients needing private supply regardless of which TPO-RA class is clinically selected.
FAQ 2: How does Manchester's diverse South Asian community experience ITP and does ELTROMBYRA 25mg dosing differ?Manchester's large South Asian community — primarily Bangladeshi in Longsight and Pakistani in Rusholme and Levenshulme — has specific ITP considerations. H. pylori prevalence in South Asian communities can be a contributing factor in some ITP cases — Manchester haematologists routinely test for H. pylori (urea breath test or stool antigen) in newly diagnosed ITP in South Asian patients, as H. pylori eradication can produce significant platelet recovery without requiring TPO-RA therapy in H. pylori-associated ITP. Pharmacogenomic dosing variation: East Asian patients (also significant in Manchester's Chinese community) have documented higher Eltrombopag exposure at equivalent doses due to UGT1A1 and OATP1B1 genetic polymorphisms — FDA labelling recommends starting at 25mg every other day rather than 25mg daily for East Asian patients with ITP. For South Asian patients (Indian, Pakistani, Bangladeshi), no specific dosing adjustment is currently recommended — starting at ELTROMBYRA 25mg daily and escalating based on platelet response. Manchester haematologists apply ethnic-specific dosing guidance from NICE TA221 and the TPO-RA prescribing guidelines, with Chinese and other East Asian Manchester patients starting at reduced frequency before standard dosing escalation.
FAQ 3: What is the evidence for ELTROMBYRA 25mg in secondary ITP caused by conditions common in Manchester?Not all ITP is idiopathic (primary) — secondary ITP occurs in association with underlying conditions that must be diagnosed and treated. In Manchester's patient population, common secondary ITP associations include: HIV infection — relevant in Manchester's LGBTQ+ community where HIV-associated ITP occurs from immune dysregulation; antiviral therapy for HIV often improves platelet counts, but refractory HIV-ITP may require ELTROMBYRA. Hepatitis C — HCV-associated ITP is treated with DAA HCV cure, which resolves ITP in many cases; but Eltrombopag has a specific FDA approval for HCV-associated thrombocytopenia to allow interferon-based therapy initiation (now largely historical). Systemic lupus erythematosus (SLE) — more prevalent in Manchester's South Asian and African Caribbean female populations; SLE-associated ITP requires lupus treatment alongside TPO-RA. Antiphospholipid syndrome — associated with ITP but also with thrombosis risk, creating an unusual scenario where raising platelets with ELTROMBYRA in APS-ITP may paradoxically increase thrombosis risk from platelet count-driven thrombosis. Manchester's MRI haematologists thoroughly evaluate all ITP patients for secondary causes before treating with ELTROMBYRA — addressing the underlying condition alongside TPO-RA as appropriate.
FAQ 4: What occupational implications does ITP with low platelets have for Manchester's working population and how does ELTROMBYRA help?ITP significantly impacts occupational capacity — particularly for Manchester's large manufacturing, construction, nursing, and manual labour workforce. Specific occupational ITP concerns: healthcare workers with very low platelet counts (below 30 × 10⁹/L) may require exclusion from invasive procedures and patient contact situations involving blood exposure risk; construction workers face trauma risk from fall or tool injuries where thrombocytopenia dramatically worsens bleeding severity; nursing staff at Manchester's NHS trust handling patients during resuscitation or venepuncture face occupational blood exposure where ITP-related prolonged bleeding from skin breaks is a concern; and drivers of heavy goods vehicles or passenger transport may face DVLA restrictions when platelet counts are dangerously low. ELTROMBYRA 25mg raising Manchester ITP patients' platelet counts into the 50-100 × 10⁹/L target range directly enables continued occupational participation — maintaining financial security and psychological wellbeing that are central to quality of life for Manchester's working-age ITP population. Manchester's occupational health services at major employers (NHS Manchester, the NHS Trust) work with haematology to assess fitness for specific occupational tasks based on current platelet count — ELTROMBYRA-controlled ITP typically enables full work participation at platelet counts above 50 × 10⁹/L.
FAQ 5: How does Manchester's NHS ELTROMBYRA prescribing process work and where does private supply through Unnati Pharmax fit?Eltrombopag (Revolade/ELTROMBYRA) is available on NHS England through NICE TA221 (chronic severe ITP refractory to first-line treatment) — prescribed by specialist haematologists, administered through specialist pharmacy, and dispensed as a Homecare Medicine direct to patient's home in many cases. Manchester Royal Infirmary's haematology pharmacy coordinates with homecare providers to supply Revolade to Manchester's eligible ITP patients. NHS supply gaps or circumstances where Unnati Pharmax serves Manchester patients: patients in the assessment period before NICE TA221 criteria are formally confirmed (up to several months); patients who have transitioned haematology provider and face prescribing continuity gaps; patients with borderline criteria who are managed on a consultant's clinical judgement but don't meet formal NICE criteria — where private supply is the only option; patients whose Homecare delivery has failed (logistical issue with homecare provider); and patients seeking supply during temporary NH restrictions. Manchester patients accessing ELTROMBYRA from Unnati Pharmax should maintain their Manchester Royal Infirmary haematology team involvement for clinical monitoring (platelet counts, liver function, ophthalmology assessments) — even while sourcing medication privately. Our WHO-GMP certified ELTROMBYRA 25mg meets the quality standards that Manchester's haematologists expect for their patients' treatment.