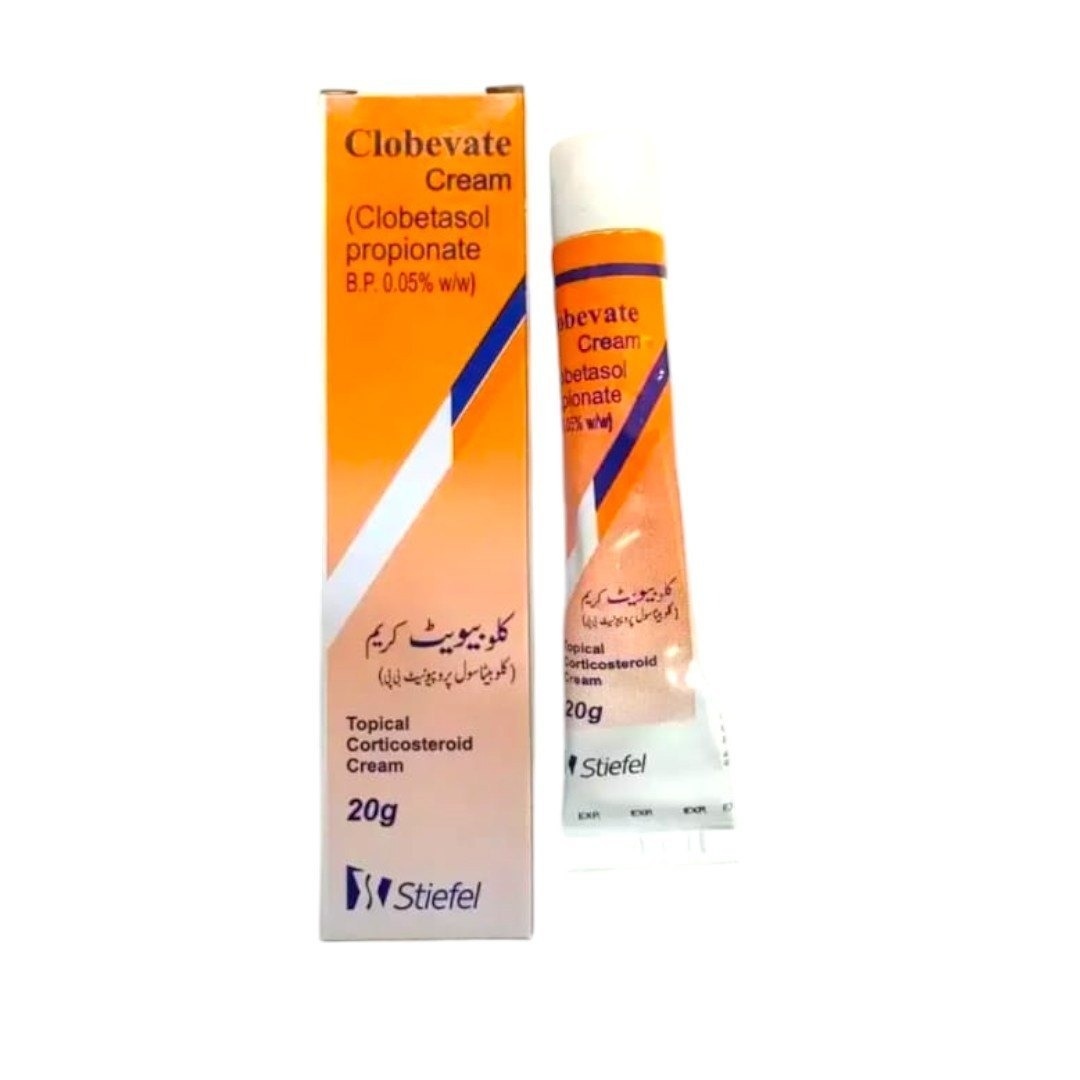
Boston's academic medical community — Harvard Medical School, MGH, Brigham and Women's, and BIDMC — serves complex dermatology patients requiring potent topical steroid therapy for severe eczema, psoriasis, and other inflammatory skin conditions. Clobevate Cream (Clobetasol 0.05%) is the most potent class I topical corticosteroid, reserved for severe dermatological conditions unresponsive to milder treatments. Unnati Pharmax supplies Clobevate to Boston patients requiring affordable potent corticosteroid at dramatically reduced cost.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: Why is Clobetasol 0.05% in Clobevate classified as a Class I potent corticosteroid and what does this mean for Boston patients?
Topical corticosteroids are classified by potency from Class I (superpotent) to Class VII (lowest potency). Clobetasol propionate 0.05% sits at Class I — the most potent available — based on vasoconstriction assay data and clinical evidence demonstrating superior efficacy versus all lower-class steroids. Class I potency means: maximum anti-inflammatory effect for suppressing severe inflammation in conditions like psoriasis, discoid lupus, lichen planus, and severe eczema; rapid clinical response typically within 48-72 hours versus weeks for milder steroids; and greater systemic absorption risk requiring careful use protocols. Boston's academic dermatologists prescribe Clobevate specifically for: short-course (2-4 week maximum per site) treatment of severe flares; thick-skin areas (palms, soles, scalp) where milder steroids penetrate inadequately; and conditions specifically requiring superpotent anti-inflammatory effect to achieve response. The prescribing discipline of Boston's Harvard-affiliated dermatologists ensures appropriate use — Clobevate is a powerful clinical tool when used correctly, not a casual first-line treatment.
FAQ 2: What are the risks of overusing Clobevate (Clobetasol 0.05%) and how do Boston dermatologists prevent them?Class I corticosteroids have significant risks with overuse or prolonged application. Local risks: skin atrophy — thinning of the dermis from suppression of collagen synthesis, producing fragile, paper-thin skin particularly at delicate sites (face, genitals, skin folds); striae (stretch marks) from skin thinning; telangiectasia (visible capillary dilation) from steroid-induced vessel fragility; perioral dermatitis or steroid rosacea from facial use; and acneiform eruptions. Systemic risks: significant systemic absorption from Clobetasol (particularly under occlusion, from large surface area application, or from intertriginous areas) can cause HPA axis suppression — measurable cortisol suppression occurs with as little as 7g/week under occlusion; Cushing's syndrome features with prolonged large-area use; and growth suppression in children. Boston dermatologists prevent these risks through: maximum 2-4 week continuous use at any site; avoiding face, groin, axillae application unless absolutely necessary with shorter courses; no occlusion (wrapping) without specialist oversight; and regular review with transition to maintenance steroid-free or lower-potency regimens after acute control.
FAQ 3: How does Clobevate Cream treat severe discoid eczema in Boston's eczema patient population?Discoid (nummular) eczema — characterised by coin-shaped intensely itchy, oozing, or crusting plaques that are notoriously resistant to milder treatments — responds well to Clobetasol 0.05% in Clobevate. The pathophysiology of discoid eczema involves an intensely dysregulated Th2/Th1 inflammatory response in the dermis that produces thick, resistant plaques on lower limbs, trunk, and arms. Milder corticosteroids (Class IV-VI) often produce minimal benefit in established discoid lesions — the dense dermal inflammation requires superpotent anti-inflammatory intervention. Clobevate directly suppresses this inflammatory cascade through glucocorticoid receptor-mediated gene transcription changes — reducing cytokine production (IL-4, IL-13, IL-31), mast cell degranulation, and eosinophil infiltration. Boston's MGH dermatology eczema clinic uses Clobevate for acute severe discoid flares: twice-daily application for 2-4 weeks to achieve lesion clearance, then transitioning to a lower-potency maintenance corticosteroid or steroid-sparing agents like calcineurin inhibitors (tacrolimus, pimecrolimus) for maintenance.
FAQ 4: What is topical steroid withdrawal (TSW) and how does responsible Clobevate prescribing prevent it?Topical steroid withdrawal (TSW) — also called "Red Skin Syndrome" — is a poorly understood but clinically documented phenomenon occurring after cessation of long-term, frequent topical corticosteroid use. Symptoms include: rebound intense skin redness and burning extending beyond original treatment areas; severe itch; skin weeping and crusting; and temperature dysregulation — occurring days to weeks after stopping prolonged topical steroid use. TSW is most associated with Class I steroids used on the face and sensitive areas for extended periods. The mechanism involves skin vasodilation rebound after steroid-induced vasoconstriction, and possibly HPA axis-related skin cortisol deficiency. Boston's dermatologists prevent TSW through: strict 2-4 week maximum continuous use per site; scheduled breaks between courses; avoiding Class I steroids on the face unless specifically indicated with very short courses; tapering to lower-potency steroids rather than abrupt cessation; and educating Boston patients about stopping at the prescribed endpoint rather than continuing indefinitely for cosmetic smoothness.
FAQ 5: How is Clobevate used as part of the "Weekend Therapy" protocol for psoriasis at Boston's academic dermatology centres?Weekend therapy (or pulse therapy) is a validated maintenance protocol specifically developed to preserve Clobetasol's efficacy while avoiding the continuous-use risks described above. The protocol: after achieving initial clearance of psoriasis plaques with daily Clobevate use (2-4 weeks), transition to weekend-only application — Clobevate applied on Saturday and Sunday only, with the skin resting from steroids during weekdays. This intermittent approach maintains remission in many psoriasis patients while dramatically reducing total steroid exposure compared to daily use — reducing atrophy risk, HPA axis suppression risk, and tachyphylaxis (the progressive loss of response seen with continuous potent steroid use). Boston's Brigham and Women's psoriasis programme uses this weekend therapy protocol as their standard maintenance approach after achieving initial Clobevate-induced clearance — it produces 6-12 month remission maintenance with significantly reduced toxicity compared to continuous use. Some protocols use Clobevate for two consecutive weekend days; others alternate weekends; the specific approach is individualised to disease severity and patient adherence patterns.