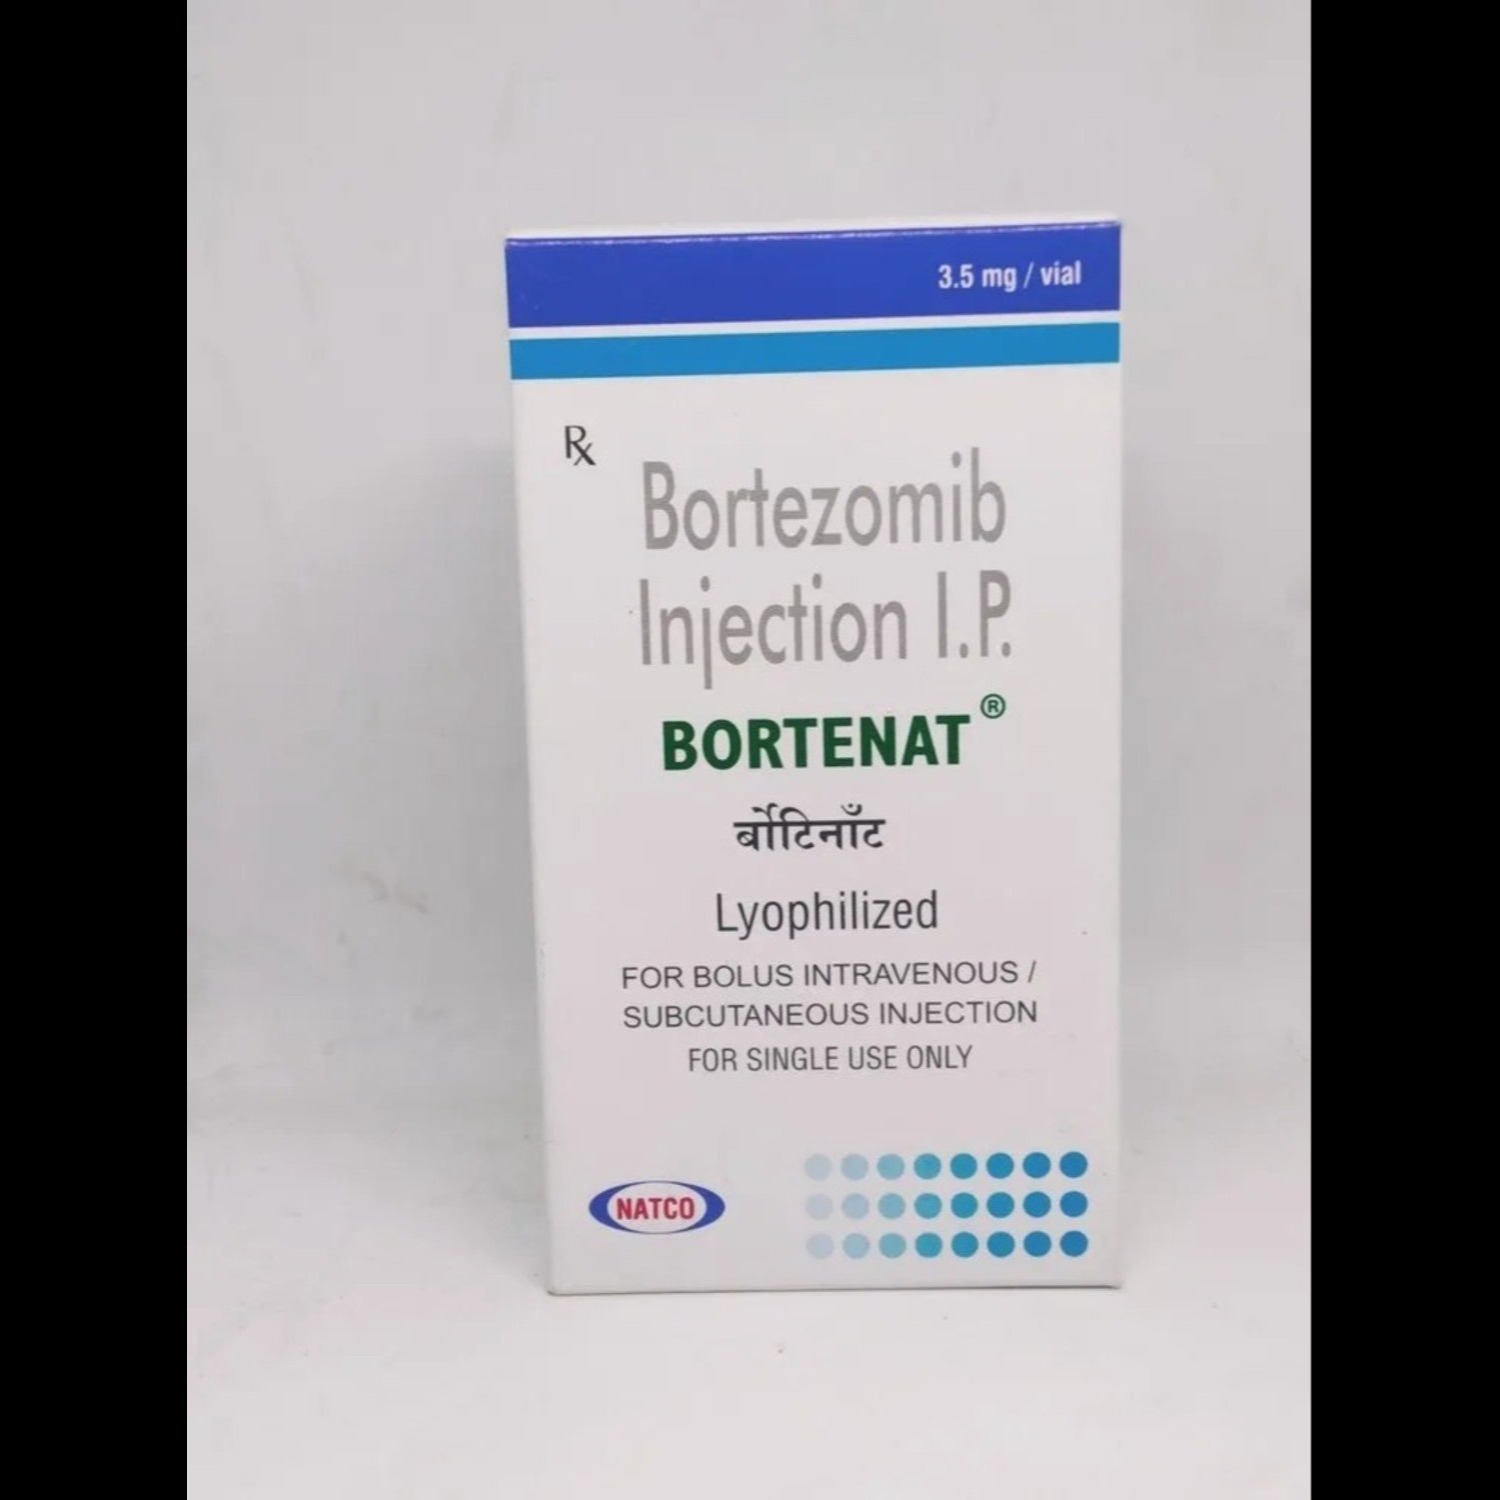
Washington DC's Georgetown University Medical Center, MedStar Georgetown Cancer Institute, and Howard University Cancer Center manage myeloma, lymphoma, and amyloidosis patients requiring Bortezomib-based therapy. Bortenat 3.5mg from Unnati Pharmax offers DC institutional pharmacy procurement teams competitive B2B pricing with complete WHO-GMP documentation supporting compliance team evaluation.
 FAQ 1: What is the difference between myeloma and lymphoma — can Bortenat treat both? FAQ 2: What is the response assessment schedule for myeloma patients on Bortenat-based therapy at DC cancer centres? FAQ 3: What is the role of Bortenat in treating light chain (AL) amyloidosis at DC medical centres? FAQ 4: How are myeloma patients monitored for Bortenat's effects on autonomic neuropathy? FAQ 5: What is the role of bispecific antibodies in myeloma and how might they complement Bortenat in future DC practice?
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
FAQ 1: What is the difference between myeloma and lymphoma — can Bortenat treat both?Multiple myeloma and lymphoma are both cancers of lymphoid cells but arise from different cell types and manifest differently. Myeloma arises from terminally differentiated plasma cells in the bone marrow, producing excessive monoclonal immunoglobulin (M-protein) and causing bone damage, anaemia, and kidney disease. Lymphoma arises from earlier lymphoid precursors — either B-cells (most common), T-cells, or NK cells — typically manifesting as lymph node enlargement, spleen involvement, and less frequently bone marrow disease. Bortezomib (Bortenat) is approved for myeloma and mantle cell lymphoma — a specific aggressive B-cell lymphoma subtype. In mantle cell lymphoma, Bortenat is used as part of salvage regimens (particularly the BR + Bortezomib combination) and has demonstrated significant activity. DC's haematologists at Georgetown manage both myeloma and MCL with Bortenat, applying disease-specific protocols for each.
FAQ 2: What is the response assessment schedule for myeloma patients on Bortenat-based therapy at DC cancer centres?Response assessment for myeloma follows IMWG (International Myeloma Working Group) criteria. Serum and urine M-protein measurements and free light chain ratios are assessed before each cycle (every 3-4 weeks during induction). Responses are classified as: Complete Response (CR — no detectable M-protein by standard electrophoresis), Very Good Partial Response (VGPR — 90%+ reduction), Partial Response (PR — 50%+ reduction), Minimal Response (MR), Stable Disease (SD), or Progressive Disease (PD). After induction with Bortenat-based regimens (typically 4-6 cycles), a comprehensive response assessment including bone marrow biopsy and MRD testing guides decisions about proceeding to transplant or maintenance. DC's Georgetown haematology team presents all complex response assessment cases at multidisciplinary tumour boards to ensure optimal treatment decisions are made with full specialist input.
FAQ 3: What is the role of Bortenat in treating light chain (AL) amyloidosis at DC medical centres?AL amyloidosis occurs when abnormal plasma cells produce light chain proteins that misfold and deposit as amyloid fibrils in organs — particularly the heart (causing cardiomyopathy), kidneys (causing nephrotic syndrome), nerves, liver, and gut. The treatment principle mirrors plasma cell myeloma: eliminate the abnormal plasma cell clone to stop amyloid production, halting organ damage progression. Bortezomib (Bortenat)-based regimens — particularly VCd (Bortezomib + Cyclophosphamide + Dexamethasone) — are the cornerstone of frontline AL amyloidosis treatment, producing rapid haematological responses that stop new amyloid deposition. The challenge unique to AL amyloidosis is cardiac involvement — amyloid cardiomyopathy makes patients more susceptible to drug toxicity, requiring careful dose adjustment. Georgetown's cardio-oncology programme provides specialised cardiac management for DC's AL amyloidosis patients receiving Bortenat-based therapy.
FAQ 4: How are myeloma patients monitored for Bortenat's effects on autonomic neuropathy?Beyond peripheral sensory neuropathy (numbness and tingling in hands and feet), Bortezomib (Bortenat) can cause autonomic neuropathy — affecting the involuntary nervous system. Autonomic effects include orthostatic hypotension (dizziness on standing due to impaired blood pressure regulation), gastroparesis (delayed gastric emptying causing nausea, bloating, early satiety), constipation from reduced gut motility, and rarely urinary retention. DC's oncology teams monitor for autonomic neuropathy through patient symptom reporting — asking specifically about dizziness when standing, gastrointestinal symptoms, and urinary difficulties at each visit. Orthostatic hypotension from Bortenat can compound the dexamethasone-induced fluid shifts and the underlying neuropathy that myeloma itself can cause. Management includes hydration guidance, compression stockings for orthostatic hypotension, laxative use for constipation, and dose modification if autonomic symptoms are severe.
FAQ 5: What is the role of bispecific antibodies in myeloma and how might they complement Bortenat in future DC practice?Bispecific antibodies represent one of the most exciting advances in myeloma treatment since CAR-T cells. These engineered antibodies simultaneously target a myeloma antigen (BCMA, GPRC5D, or FcRH5) and the CD3 receptor on T cells — physically bringing T cells into contact with myeloma cells to trigger killing. Approved bispecifics including Teclistamab (BCMA × CD3), Elranatamab, and Talquetamab (GPRC5D × CD3) have shown remarkable response rates in heavily pre-treated relapsed/refractory myeloma. Georgetown's haematologists are participating in clinical trials evaluating bispecifics in earlier treatment lines — including combinations with proteasome inhibitors like Bortenat. The emerging treatment landscape sees bispecifics potentially combined with Bortezomib-based regimens in second and third line myeloma before considering CAR-T, potentially extending the overall treatment armamentarium and delaying the need for intensive cellular therapies. DC patients interested in these novel approaches should discuss clinical trial eligibility with their Georgetown haematologist.