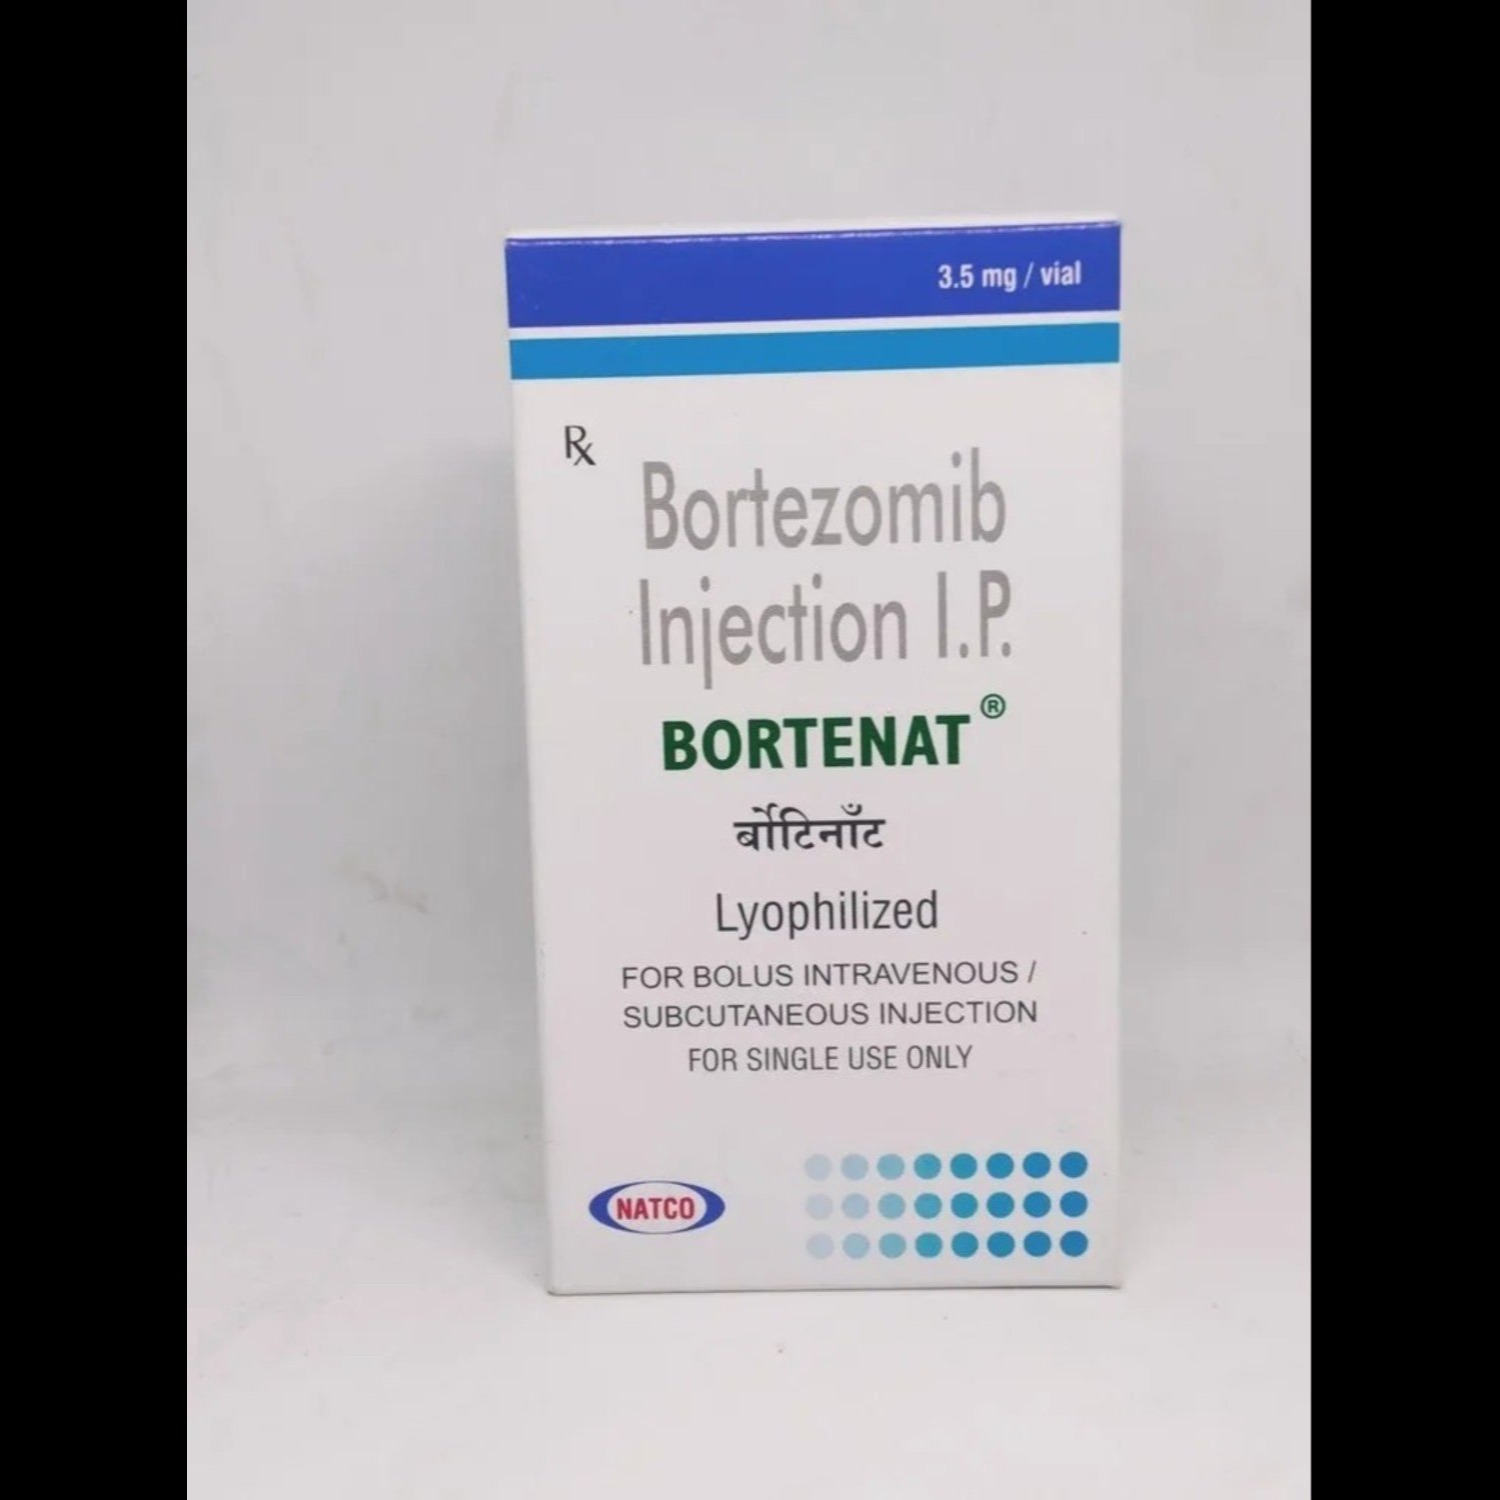
Toronto's Princess Margaret Cancer Centre — consistently ranked among the world's top cancer centres — manages one of Canada's largest myeloma patient populations. Ontario's extraordinary ethnic diversity — with large South Asian, East Asian, Caribbean, and African communities — means myeloma presents across a wide demographic spectrum with varying disease biology. Bortenat 3.5mg provides Toronto's myeloma patients with affordable Bortezomib at dramatically reduced institutional and private cost versus brand Velcade Ontario pricing.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: How does myeloma biology differ across Toronto's diverse ethnic communities — are outcomes different?
Myeloma exhibits meaningful biological differences across ethnic groups — with important clinical implications for Toronto's remarkably diverse patient population. African descent: Black Canadians have approximately 2-fold higher myeloma incidence than white Canadians; tend to present at younger ages; have distinct cytogenetic profiles with higher rates of the translocation t(11;14) which may predict better response to venetoclax-containing regimens; and historically have had lower clinical trial enrolment, limiting ethnicity-specific outcome data. MGUS (monoclonal gammopathy of undetermined significance) — the precursor to myeloma — is also more prevalent in Black populations. South Asian populations: emerging data suggests distinct myeloma presentation patterns; genetic risk variants differ between South and East Asian versus European ancestry populations. East Asian (Chinese, Japanese, Korean) populations in Toronto: some data suggests different cytogenetic distributions. Princess Margaret's myeloma programme has prioritised ethnically diverse clinical research — Toronto's extraordinary diversity makes it ideally positioned to generate the ethnicity-specific myeloma outcome data that can guide personalised treatment for global populations. Bortenat 3.5mg is clinically relevant across all these ethnic presentations — Bortezomib's proteasome inhibition mechanism is cytogenetics-agnostic and effective across myeloma's biological diversity.
FAQ 2: How does Ontario's cancer drug funding programme (CDFP) cover Bortenat and what gaps exist?Ontario's Cancer Care Ontario administers the Cancer Drug Funding Program (CDFP) — providing cancer medications including Bortezomib (Velcade) to eligible Ontario residents. CDFP coverage for Bortezomib: approved for newly diagnosed and relapsed multiple myeloma, and mantle cell lymphoma, in specific regimen combinations recommended by Cancer Care Ontario's drug advisory committee. Coverage is administered through Ontario's regional cancer centres and community oncology programmes. Gaps in CDFP Bortenat access: patients who require Bortezomib as part of an investigational regimen not yet CDFP-approved; patients whose employer drug plan has high co-payments that make CDFP-covered drugs cost-shared at significant patient expense; patients in the non-resident international student or temporary visa category without OHIP; and patients whose care is managed through private oncology where CDFP dispensing logistics create delays. For Toronto myeloma patients in these gaps, Bortenat 3.5mg from Unnati Pharmax at dramatically reduced cost provides supply continuity — ensuring treatment isn't delayed or interrupted while coverage questions are resolved. Princess Margaret's pharmacy team can advise on CDFP eligibility and appropriate private supply pathways for patients outside CDFP coverage.
FAQ 3: What is the VCd regimen for AL amyloidosis in Toronto and how central is Bortenat to it?AL amyloidosis — where aberrant plasma cells produce light chain proteins that misfold and deposit as amyloid fibrils in organs — shares treatment principles with myeloma: eliminating the clonal plasma cell population to stop amyloid production. Toronto's Princess Margaret manages AL amyloidosis patients through a dedicated amyloid programme in collaboration with cardiology at Toronto General Hospital (where cardiac amyloidosis — the most serious manifestation — is managed with TGH's advanced heart failure programme). The VCd regimen (Bortezomib + Cyclophosphamide + Dexamethasone) is frontline for AL amyloidosis at Princess Margaret — Bortezomib (Bortenat 3.5mg) is the backbone, achieving haematological complete response rates of 40-60% in newly diagnosed AL amyloidosis. The critical clinical challenge unique to AL amyloidosis: cardiac involvement dramatically increases treatment-related toxicity risk — patients with advanced cardiac amyloidosis tolerate dexamethasone poorly (fluid retention) and Bortezomib at standard doses may require reduction; the cardiac amyloidosis-specific risks include arrhythmia and haemodynamic instability from the amyloid cardiomyopathy context. Princess Margaret's amyloid team works with TGH cardiologists for every AL amyloidosis patient — cardiac function assessment guides Bortenat dosing decisions throughout the VCd course.
FAQ 4: How does subcutaneous Bortenat administration reduce neuropathy in Toronto's myeloma patients?As established in the pharmacology literature and confirmed in Princess Margaret's clinical practice: subcutaneous (SC) Bortezomib administration significantly reduces peripheral neuropathy versus intravenous (IV) administration — Grade 3-4 neuropathy occurring in approximately 6% (SC) versus 16% (IV) in the pivotal MMY-3021 comparison trial. Princess Margaret's myeloma programme routinely uses SC Bortenat as the default route — administering via subcutaneous injection alternating between the abdomen and thigh. The reduced neuropathy with SC reflects lower peak plasma concentrations (lower Cmax with SC compared to bolus IV) while maintaining equivalent overall drug exposure (similar AUC). For Toronto myeloma patients with pre-existing peripheral neuropathy from diabetes, prior vincristine exposure, or hereditary neuropathy, Princess Margaret begins at reduced SC dosing (1.0mg/m² rather than 1.3mg/m²) with careful monitoring — using standardised neuropathy grading (NCI CTC AE) at every clinic visit. The neuropathy reduction with SC Bortenat makes a meaningful difference to quality of life in Toronto's active professional and older myeloma population — maintaining hand function, balance, and daily activity capacity that IV-associated neuropathy frequently compromises.
FAQ 5: What is the evidence for Bortenat in treating Waldenstrom's macroglobulinaemia in Toronto?Waldenström's macroglobulinaemia (WM) — a lymphoplasmacytic lymphoma characterised by bone marrow infiltration and secretion of monoclonal IgM — shares some pathological features with myeloma and responds to some overlapping treatments. Bortezomib (Bortenat 3.5mg) has meaningful activity in WM, particularly in combination regimens. The BDR regimen (Bortezomib + Dexamethasone + Rituximab) demonstrates response rates of 80-90% in newly diagnosed WM patients — established as an effective chemoimmunotherapy option. However, WM treatment has been transformed by BTK inhibitors — Ibrutinib and Zanubrutinib have demonstrated superior long-term disease control for most WM patients, and Toronto's Princess Margaret now positions BTK inhibitors as the preferred frontline approach for most symptomatic WM cases. Bortenat retains its role in WM for: patients with BTK inhibitor contraindications or intolerability; WM with specific features (bing-neel syndrome, amyloidosis) where Bortezomib-based approaches may be preferred; combination regimens as bridge therapy before BTK inhibitor initiation; and for MYD88-wild-type WM where BTK inhibitor response rates are lower and Bortezomib-based alternatives may be more relevant. Princess Margaret's lymphoma-myeloma conference discusses WM cases and individuated treatment selection in this rapidly evolving landscape.