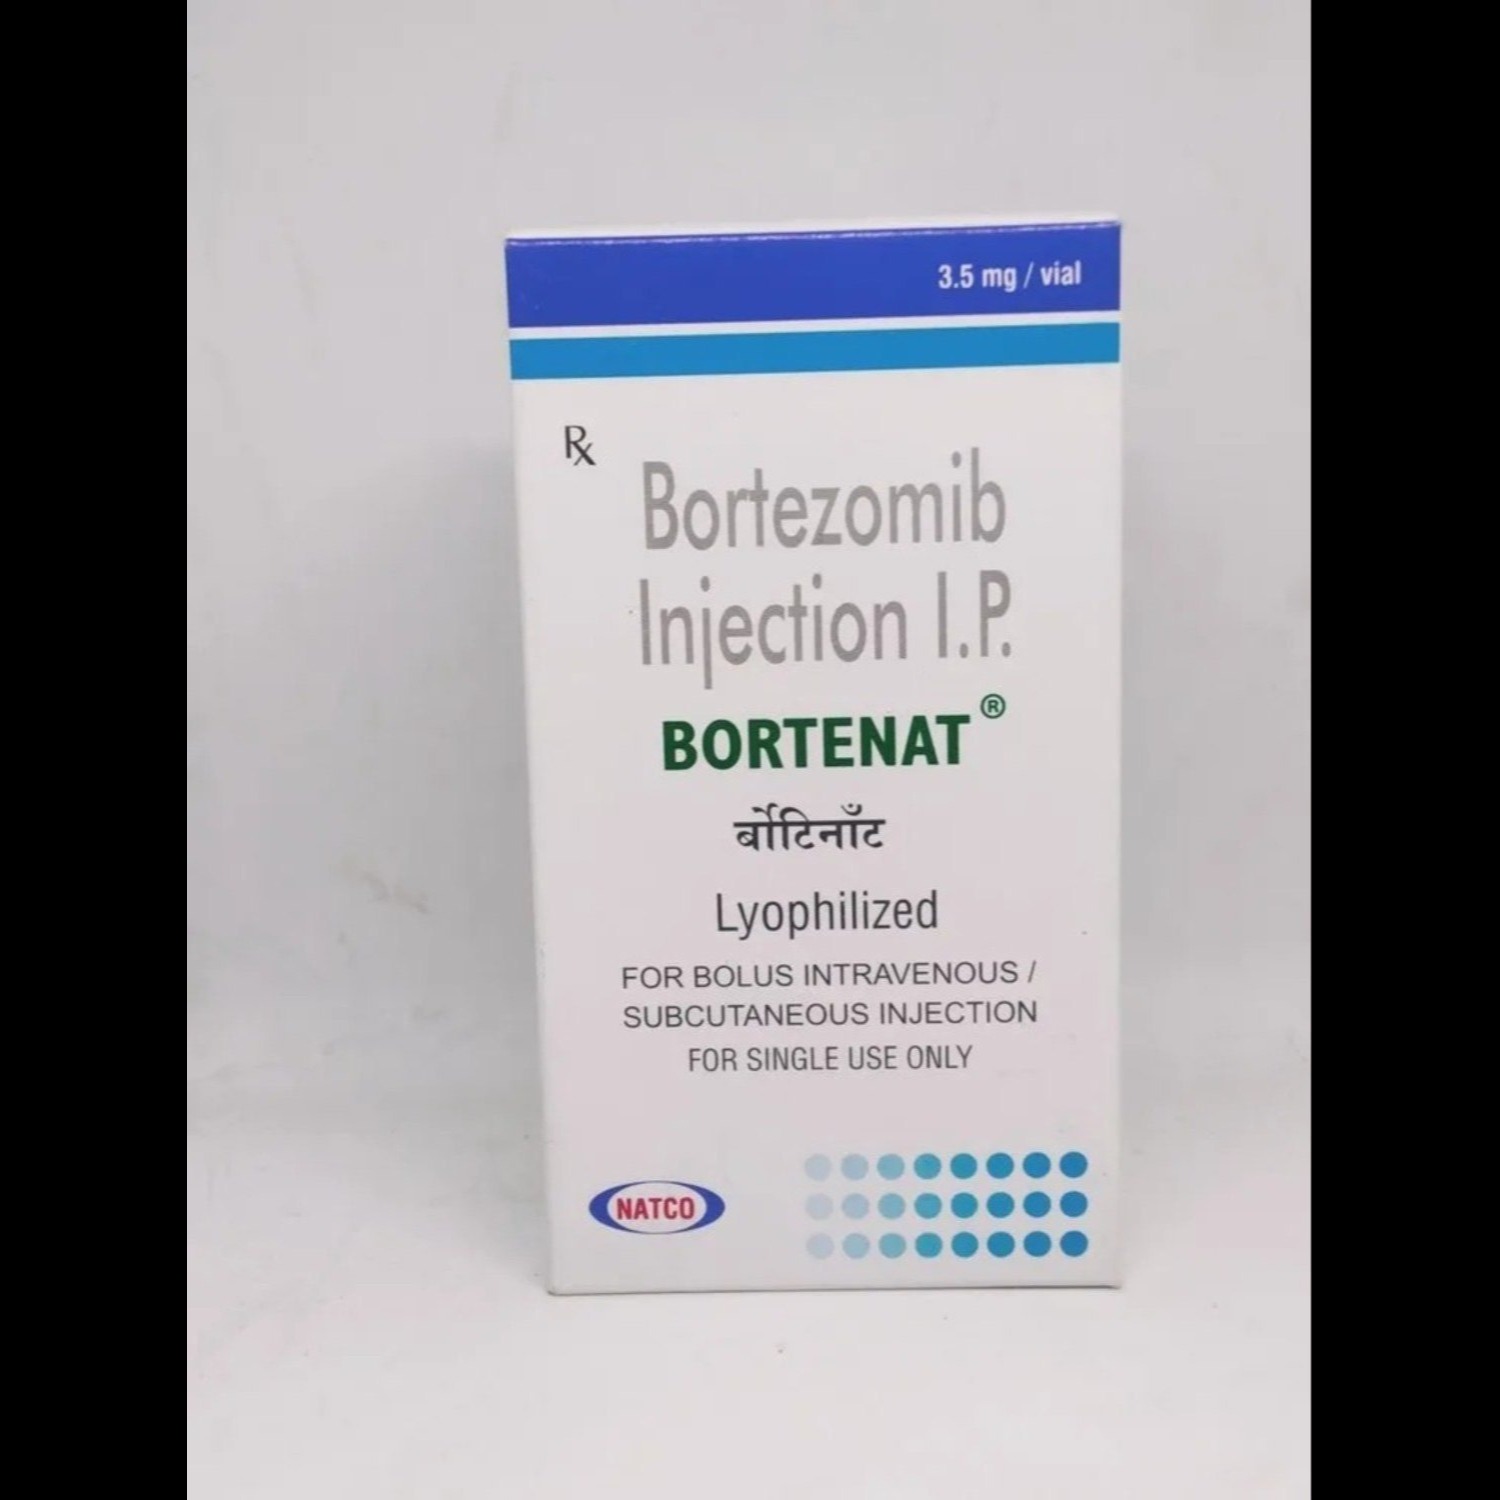
Toronto's Princess Margaret Cancer Centre — ranked among the world's top five cancer hospitals — and Sunnybrook Health Sciences Centre manage Ontario's largest myeloma and amyloidosis patient populations requiring Bortezomib-based therapy. Bortenat 3.5mg provides Toronto's institutional pharmacy procurement teams with WHO-GMP certified Bortezomib at competitive B2B pricing, and private patients with affordable access to this essential proteasome inhibitor.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
FAQ 1: What is the KRd regimen and how does Bortenat relate to carfilzomib-based therapies?KRd (Carfilzomib + Lenalidomide + Dexamethasone) uses Carfilzomib — a next-generation irreversible proteasome inhibitor — as an alternative to Bortezomib in the VRd regimen. While both Bortezomib (Bortenat) and Carfilzomib are proteasome inhibitors, they differ importantly: Bortezomib reversibly inhibits the 26S proteasome, while Carfilzomib binds irreversibly, producing more sustained proteasome inhibition and potentially greater depth of response. KRd has shown superior progression-free survival versus VRd in some patient populations (ENDURANCE trial nuances aside). However, Carfilzomib carries higher cardiovascular toxicity risk — hypertension, heart failure, and cardiac events — compared to Bortezomib. Toronto's Princess Margaret haematologists choose between Bortenat-based and Carfilzomib-based regimens based on patient cardiovascular history, trial eligibility, and response depth goals — with Bortenat generally preferred for older patients or those with cardiac comorbidities. FAQ 2: How is Bortenat reconstituted and administered correctly as a subcutaneous injection?Bortenat 3.5mg lyophilised powder must be correctly reconstituted before subcutaneous administration. For SC use: reconstitute with 1.4mL of normal saline (0.9% NaCl) to produce a 2.5mg/mL concentration (versus 3.5mg/mL for IV administration). The resulting solution is clear and colourless — any particulate matter or discolouration indicates it should not be used. The calculated dose volume (based on 1.3mg/m² standard dose) is injected subcutaneously into the thigh or abdomen — sites should be rotated with each injection, maintaining at least 2.5cm from previous injection sites and away from areas that are bruised, red, or tender. For patients self-administering at home (common in Toronto's Princess Margaret patient population), detailed written injection technique instructions and a nurse-supervised initial injection are standard. Unused reconstituted solution must be stored at 2-8°C and used within 8 hours. FAQ 3: What is the VGPR or better response rate achieved with Bortenat-based induction at Princess Margaret?Response depth achieved before autologous stem cell transplant (ASCT) is a strong predictor of long-term outcomes in myeloma. With modern Bortenat-based triple induction (VRd or VCd), Princess Margaret's haematology team achieves VGPR or better responses (90%+ reduction in M-protein) in approximately 60-80% of transplant-eligible patients before ASCT — rates that were unimaginable with older alkylating agent-based regimens from a decade ago. Adding anti-CD38 monoclonal antibodies (Daratumumab) to Bortenat-based induction (Dara-VRd) increases VGPR/CR rates further to over 85-90% in clinical trials. These deep pre-transplant responses translate to longer post-transplant remissions and higher rates of MRD negativity — the treatment goal that most strongly predicts prolonged progression-free survival. Toronto's Princess Margaret haematologists present all induction response data at multidisciplinary tumour boards to guide post-induction treatment decisions. FAQ 4: What cardiac monitoring is needed for Toronto myeloma patients on Bortenat-based therapy?Bortezomib (Bortenat) has a generally favourable cardiovascular safety profile compared to Carfilzomib, but cardiac monitoring remains important — particularly for myeloma patients who may have AL amyloidosis with cardiac involvement, prior anthracycline chemotherapy, or pre-existing cardiovascular disease. Standard cardiac monitoring for Toronto patients on Bortenat includes: baseline ECG (QTc interval — Bortezomib can rarely cause QT prolongation), baseline echocardiogram in patients with known or suspected cardiac amyloid, and clinical assessment of cardiac symptoms (shortness of breath, ankle swelling, palpitations) at each cycle. Dexamethasone — an essential component of Bortenat-based regimens — independently affects blood pressure, fluid balance, and glucose control, requiring blood pressure and glucose monitoring. Princess Margaret's cardio-oncology service provides specialised cardiac assessment for complex cases, and collaborates with the haematology team on dose modifications when cardiac toxicity occurs. FAQ 5: What is the role of daratumumab biosimilars in reducing the cost of Bortenat combination regimens in Canada?Daratumumab (Darzalex) — the anti-CD38 monoclonal antibody now incorporated into frontline myeloma regimens (Dara-VRd) at Princess Margaret — is one of the most expensive individual cancer drugs, costing approximately CAD $100,000+ annually. Biosimilars (near-identical versions of biological drugs manufactured to comparable quality standards) for Daratumumab are in development globally, with several in phase 3 trials as of 2026. When Daratumumab biosimilars reach regulatory approval and market entry in Canada — which Health Canada's biosimilar framework is designed to facilitate — the cost of Dara-VRd (Daratumumab + Bortenat + Lenalidomide + Dexamethasone) will decrease substantially, improving the cost-effectiveness of this superior regimen versus standard VRd. This trajectory mirrors what happened with Trastuzumab (Herceptin) biosimilars in breast cancer, which dramatically reduced the cost of anti-HER2 therapy across Canadian provinces. Toronto's haematologists monitor biosimilar regulatory progress closely as it will directly affect their formulary decisions for myeloma treatment.