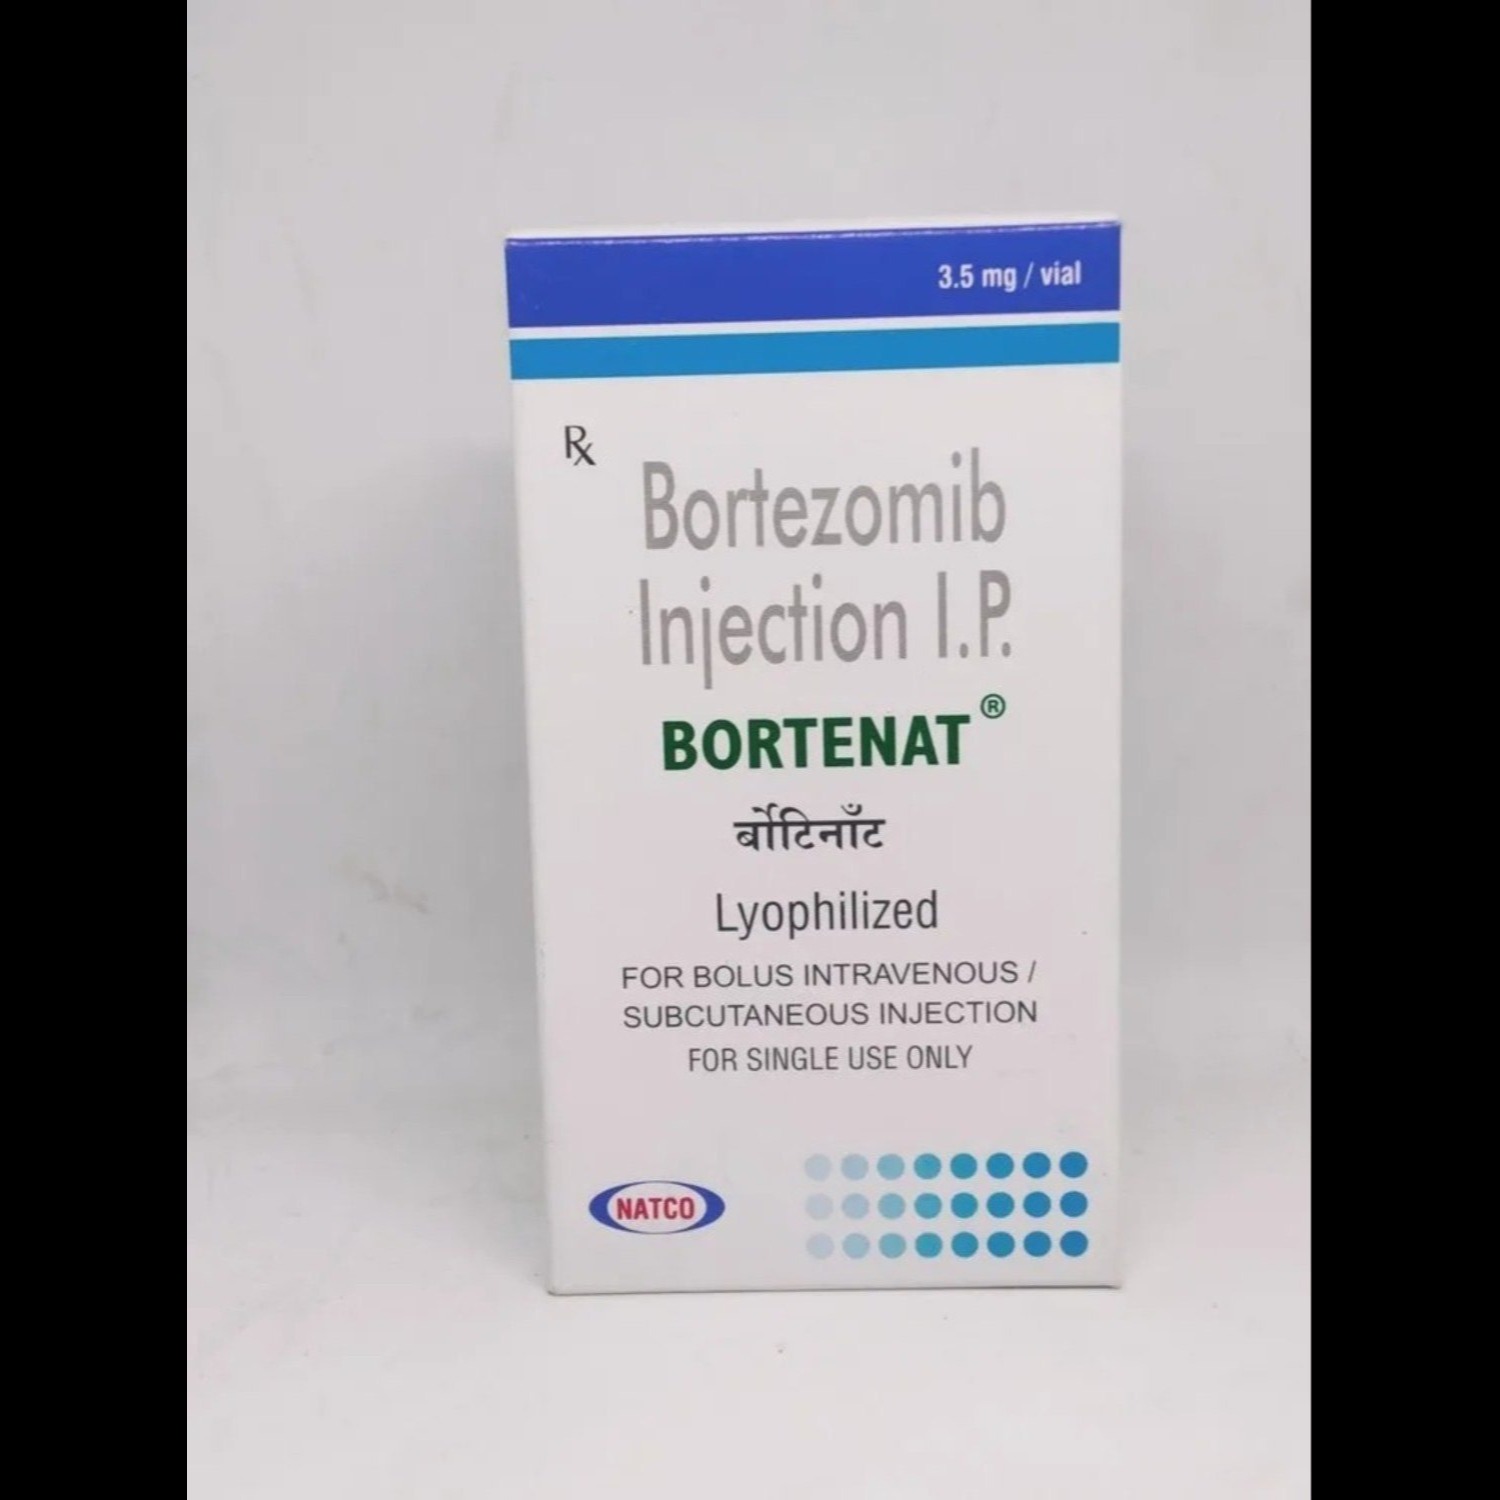
Glasgow's Beatson West of Scotland Cancer Centre — Scotland's largest cancer centre — manages myeloma, lymphoma, and amyloidosis patients from across West Scotland's 2.5 million population. Glasgow's socioeconomically diverse patient population — from affluent West End suburbs to some of Scotland's most deprived communities in the East End — creates significant disparities in cancer care engagement and treatment tolerance. Bortenat 3.5mg provides Glasgow's haematological cancer patients with affordable Bortezomib at dramatically reduced cost versus Scottish NHS private prescription pricing.
Visit unnatipharmax.com | 📱 +91 82650 41513 | 📧 Unnatipharmax@gmail.com
 FAQ 1: How does the Beatson West of Scotland Cancer Centre manage Bortenat for Glasgow's myeloma patients and what is its clinical governance model?
The Beatson West of Scotland Cancer Centre in Glasgow's Great Western Road — Scotland's largest and most comprehensively resourced cancer centre — manages haematological malignancy through its Haematology Cancer Service, which serves NHS Greater Glasgow and Clyde's 1.2 million population alongside regional referrals from Ayrshire and Arran, Forth Valley, and Highland. Beatson's Bortenat clinical governance: prescribing is guided by the Scottish Medicines Consortium (SMC) approvals and the West of Scotland Cancer Network (WOSCAN) haematology clinical management guidelines — jointly developed by Glasgow, Edinburgh, and Aberdeen haematologists to ensure Scotland-wide consistency. Bortenat 3.5mg is administered subcutaneously (SC) as the standard route at the Beatson — the SC route's superior neuropathy profile (established in the MMYVIII trial) is uniformly adopted. Beatson's myeloma multidisciplinary team (MDT) meets weekly to discuss complex cases — treatment decisions for Glasgow patients requiring Bortenat are made collectively by haematologists, clinical oncologists, specialist nurses, pharmacists, and palliative care. The Beatson's clinical pharmacy team manages Bortenat dose adjustments for peripheral neuropathy — weekly neuropathy grading and dose reduction protocols follow WOSCAN guidelines precisely. For Glasgow patients who are self-funding during gaps in NHS provision, Bortenat 3.5mg from Unnati Pharmax with WHO-GMP certification meets the quality standards that the Beatson's pharmacists require for patients continuing treatment outside NHS dispensing.
FAQ 2: How does Glasgow's significant social deprivation affect myeloma outcomes and what challenges does Bortenat present for deprived communities?Glasgow has one of Western Europe's most severe socioeconomic deprivation gradients — the Scottish Index of Multiple Deprivation (SIMD) identifies Glasgow's East End communities (Shettleston, Springburn, Parkhead) as some of Scotland's most deprived, with life expectancy gaps between Glasgow's most and least deprived areas exceeding 15 years. This deprivation context profoundly affects myeloma care. Stage at diagnosis: myeloma patients from Glasgow's most deprived communities present at later disease stages — reflecting delayed GP presentation from socially marginalised individuals who avoid healthcare systems until symptoms are severe. Treatment tolerance: malnutrition, smoking, alcohol-related liver disease, and multiple comorbidities common in Glasgow's deprived communities reduce tolerance for Bortenat's side effects — neuropathy is more pronounced in undernourished patients; haematological toxicity is exacerbated by pre-existing anaemia from nutritional deficiency. Transport barriers: the Beatson is located on Great Western Road — accessible from Glasgow's East End requires 40-60 minute public transport journeys for twice-weekly Bortenat SC injections, representing significant logistical burden for patients without transport. The Beatson's patient transport service and the West of Scotland Myeloma Nursing Team's home visit programme specifically address these access barriers — administering Bortenat in patients' homes for those who cannot travel to the Beatson. Bortenat 3.5mg from Unnati Pharmax's role is most relevant for Glasgow's self-funding patients (typically from more affluent communities) facing NHS gap periods rather than for the most deprived East End communities whose barriers are structural rather than financial.
FAQ 3: What is the VTD (Bortezomib-Thalidomide-Glasgow's Beatson haematologists face the same induction regimen debate as myeloma centres globally — whether VTD or VRD (also written RVD) is the preferred triplet for newly diagnosed myeloma patients planned for autologous stem cell transplant. VTD (Bortezomib-Thalidomide-Dexamethasone): the European standard established through the PETHEMA and GIMEMA trials — high response rate (80-90% overall response), familiar tolerability profile, thalidomide's additional anti-myeloma mechanism; preferred in some European centres including some Scottish programmes historically. VRD (RVD — Lenalidomide-Bortezomib-Dexamethasone): the US and increasingly UK/Scotland standard from SWOG S0777 and IFM2009 trials — superior progression-free survival versus VTD in direct comparison studies; excellent response rates; Lenalidomide's superior tolerability versus thalidomide (particularly neuropathy and sedation); and better maintenance compatibility (Lenalidomide can be continued as maintenance post-ASCT from the induction backbone without drug class switching). Glasgow's WOSCAN guidelines have transitioned toward VRD as preferred triplet induction — meaning Bortenat 3.5mg (Bortezomib) is used alongside Lenalid (Lenalidomide) rather than thalidomide in most new myeloma patients at the Beatson. Bortenat 3.5mg from Unnati Pharmax is specifically relevant for VRD regimens in Glasgow's self-funding context — providing the Bortezomib component at dramatically reduced cost.
FAQ 4: How does Bortenat 3.5mg treat mantle cell lymphoma in Glasgow's lymphoma patients?Mantle cell lymphoma (MCL) — an aggressive B-cell non-Hodgkin lymphoma with characteristic t(11;14) chromosomal translocation overexpressing cyclin D1 — is treated at the Beatson's lymphoma service. Bortezomib (Bortenat 3.5mg) has a specific FDA and EMA approval for relapsed MCL — the PINNACLE trial established Bortezomib's 33% overall response rate in heavily pre-treated MCL as a single agent, which is clinically meaningful in this difficult lymphoma subtype. Glasgow's Beatson lymphoma team uses Bortenat primarily in MCL treatment combinations: BR-Bortenat (Bendamustine-Rituximab + Bortezomib) for transplant-ineligible MCL patients; VR-CAP (Bortezomib-Rituximab-Cyclophosphamide-Doxorubicin-Prednisone) — the VR-CAP trial demonstrated superiority over R-CHOP for MCL in transplant-ineligible patients through proteasome inhibitor addition. The MCL treatment landscape has been significantly altered by BTK inhibitors — Ibrutinib and Zanubrutinib are now preferred for relapsed MCL, and Bortenat's role has shifted accordingly. Beatson's current MCL positioning for Bortenat: primarily in patients who have progressed on BTK inhibitors where VR-CAP or single-agent Bortezomib may salvage responses; or in combination induction for specific MCL presentations where Bortezomib's mechanism is preferred. For Glasgow's MCL patients on NHS pathways, Bortenat is provided through Beatson pharmacy; private supply through Unnati Pharmax is relevant for those in SMC approval gaps or self-funding clinical situations.
FAQ 5: What are the antiviral prophylaxis requirements for Glasgow myeloma patients on Bortenat 3.5mg?Bortezomib (Bortenat 3.5mg) reactivates Varicella-zoster virus (VZV — the herpes zoster/shingles virus) through immunosuppression of cellular immunity that normally keeps latent VZV dormant in dorsal root ganglia. Herpes zoster reactivation during Bortezomib treatment occurs in approximately 13% of patients without prophylaxis — producing the characteristic painful dermatomal rash (shingles) and potentially devastating post-herpetic neuralgia that compounds Bortezomib's neuropathy. Glasgow's Beatson mandates antiviral prophylaxis for all Bortenat-treated patients: Aciclovir 400mg twice daily (or Valaciclovir 500mg once daily as a more convenient alternative) throughout the entire Bortenat treatment course and for 3 months after completion. This prophylaxis reduces herpes zoster reactivation by over 90% in myeloma patients on Bortezomib — a near-complete protection that makes prophylaxis one of the most evidence-supported supportive care interventions in haematological oncology. Glasgow patients obtaining Bortenat 3.5mg through Unnati Pharmax must simultaneously be prescribed and adherent to antiviral prophylaxis — failure to use concurrent antiviral prophylaxis with Bortenat creates a preventable, potentially severe complication. The Beatson's haematology specialist nurses ensure all myeloma patients on Bortenat-containing regimens have Aciclovir or Valaciclovir prescribed and are counselled on its importance before beginning Bortenat treatment.